General dentistry and orthodontics — one playbook, two money engines
Engine 1: stop leaking new demand. Engine 2: make money from the chart you already have
Refine data → SOPs → workflows. Modeled ROI, labeled as a model
Soshogle Method · data you already have · Voice AI · Avatar AI · Denti-OS
Denti-OS ecosystemLive
Two engines
New patients. And the ones sitting in the chart.
Most clinics buy more ads while overdue recare, unsigned plans, and quiet patients sit in the PMS. We run both engines: capture the inquiry you already paid for, and sell the unfinished work you already diagnosed. Same method we use when a business already has years of buyers — refine the list, write the SOPs, then let workflows print the next dollar.
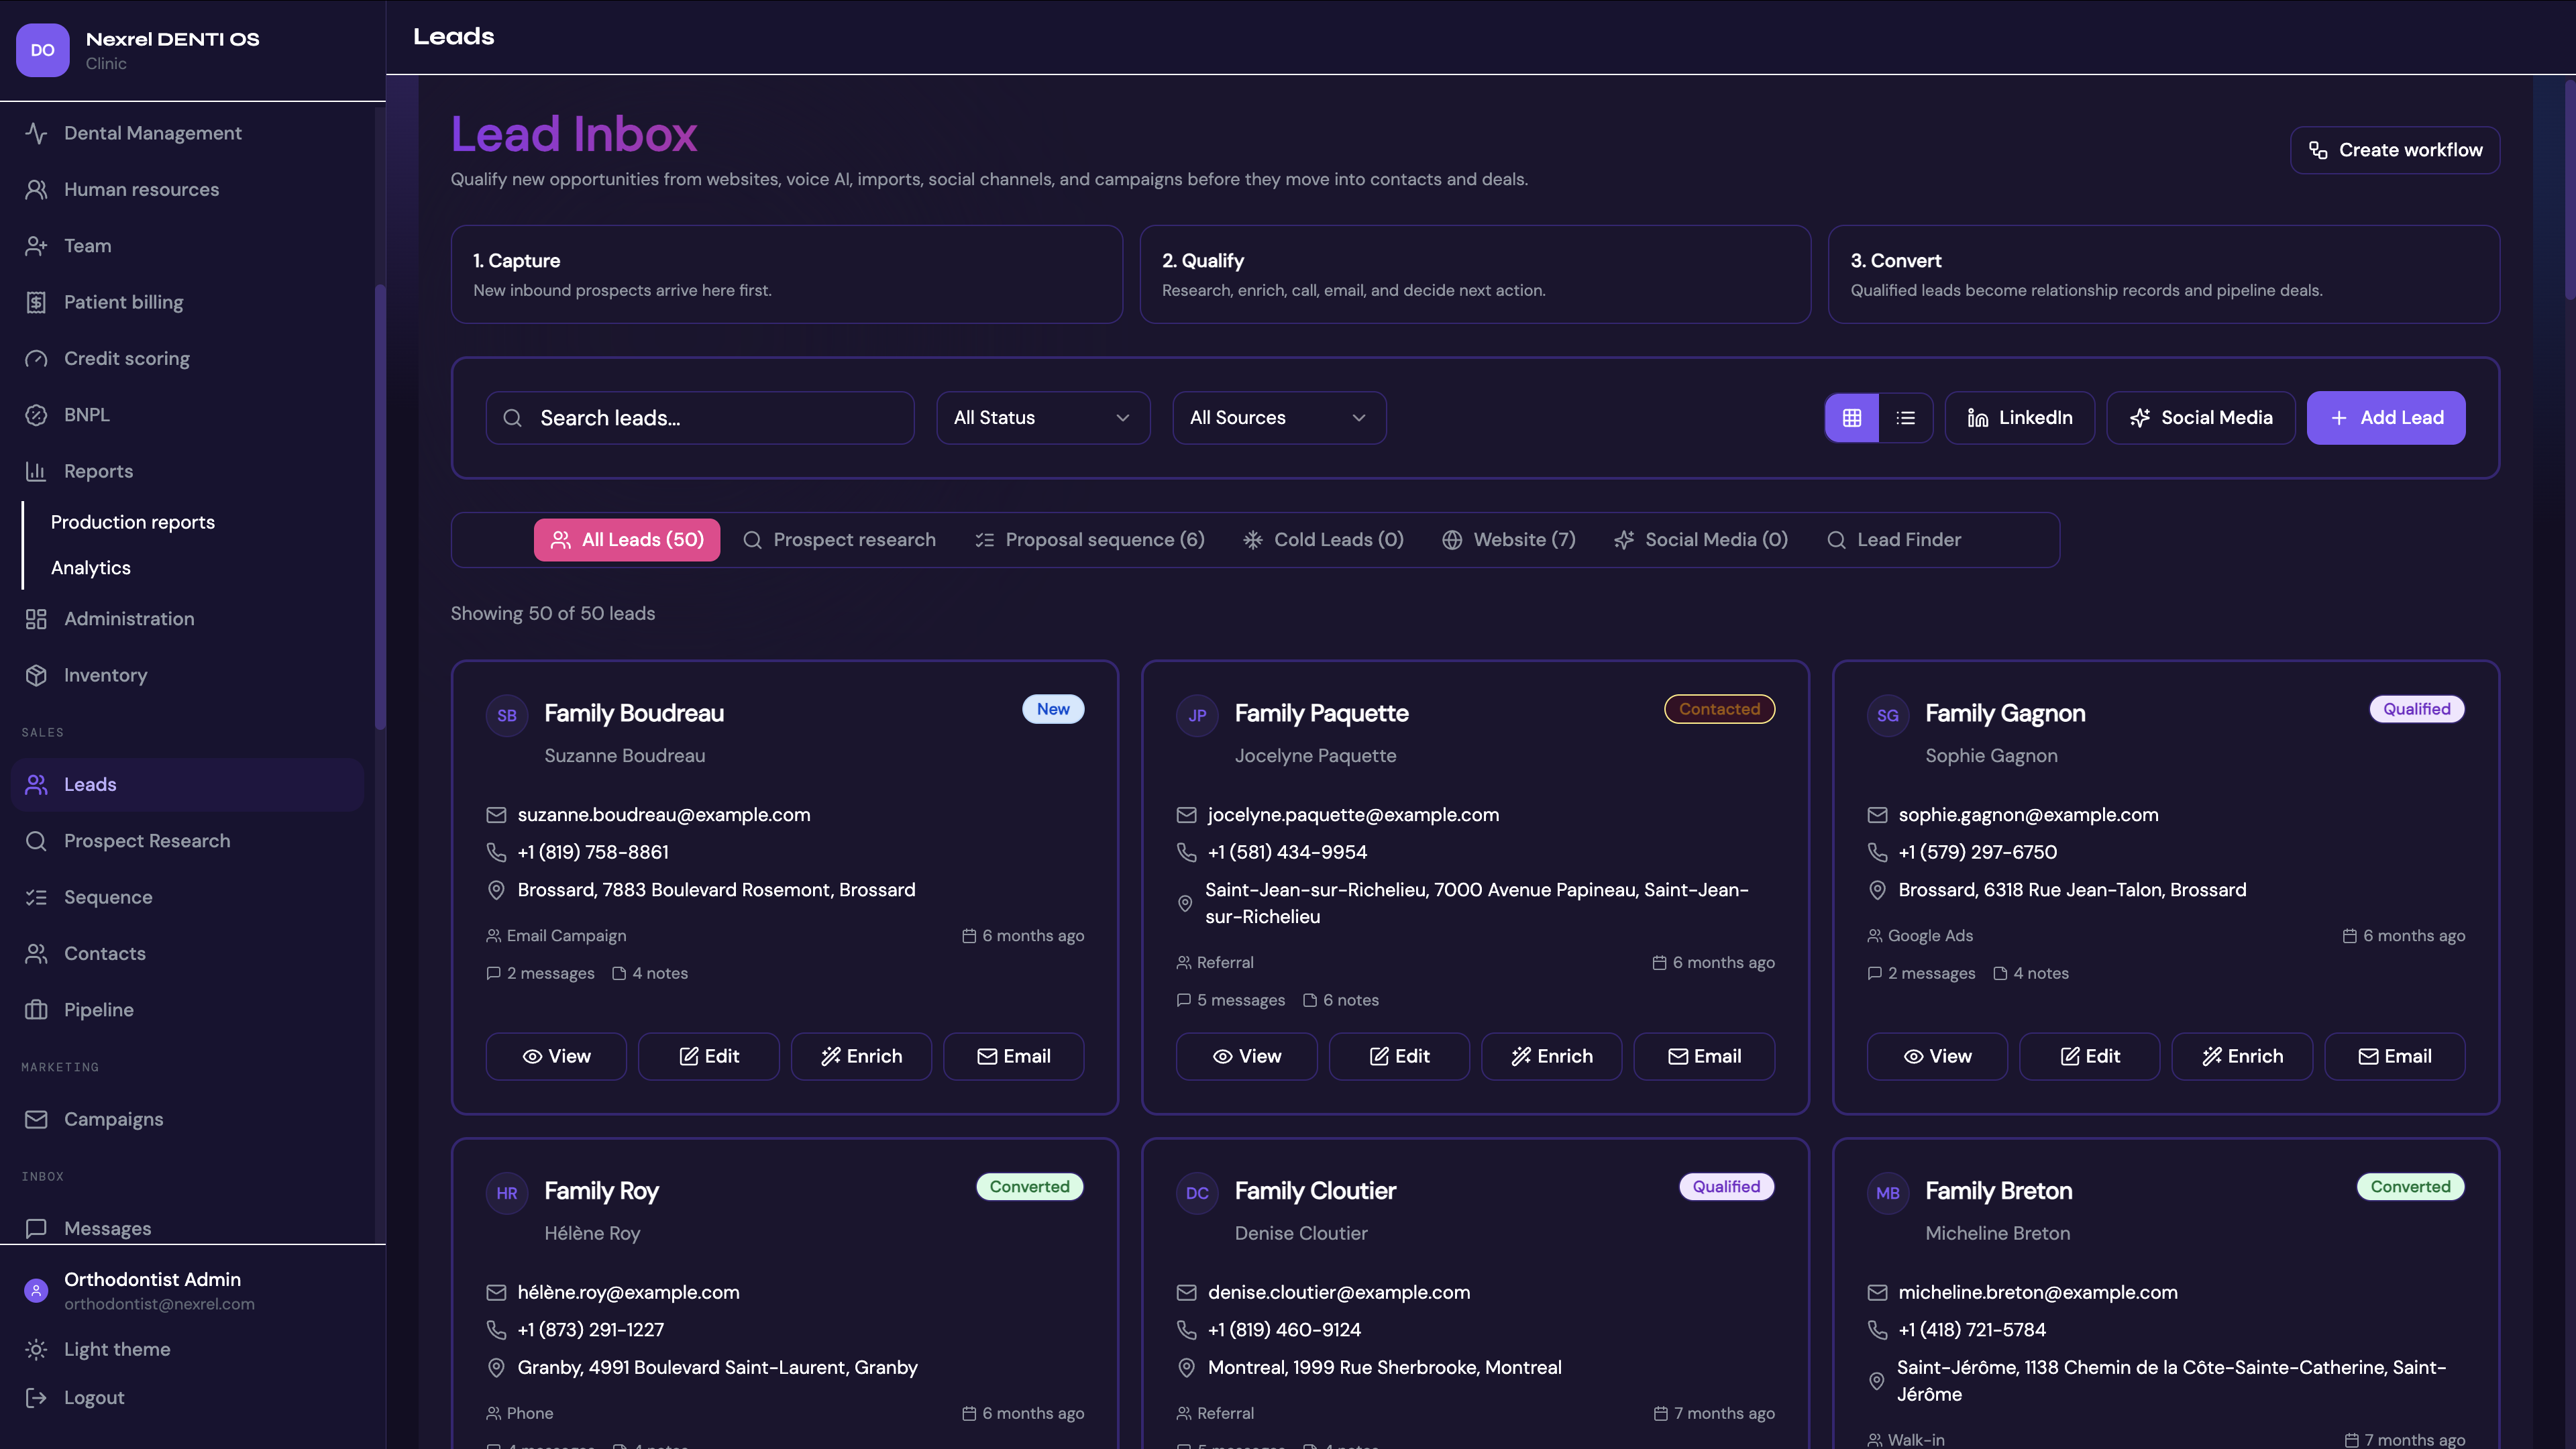
Engine 1 — ingest: website, phone, chat, Avatar AI into one CRM
Engine 2 — the chart: recare, unaccepted treatment, inactive patients, finished-ortho / family
Neither engine is a blast to the whole database. Refine first. Then three workflows, not forty campaigns
The list you already have is a gold mine and a landmine. We treat it like both.
SoshogleSOSHOGLE · NEXREL · DENTI-OS
Special issue09.2026
The dentistry Revenue Machine
Denti-OS
3×
General dentistry and orthodontics — one playbook, two money engines
Engine 1: stop leaking new demand. Engine 2: make money from the chart you already have
Refine data → SOPs → workflows. Modeled ROI, labeled as a model
Soshogle Method · data you already have · Voice AI · Avatar AI · Denti-OS
Two engines
New patients. And the ones sitting in the chart.
The list you already have is a gold mine and a landmine. We treat it like both.
Denti-OS ecosystemLive
SoshogleSOSHOGLE · NEXREL · DENTI-OS
Special issue09.2026
The dentistry Revenue Machine
Denti-OS
3×
General dentistry and orthodontics — one playbook, two money engines
Engine 1: stop leaking new demand. Engine 2: make money from the chart you already have
Refine data → SOPs → workflows. Modeled ROI, labeled as a model
Soshogle Method · data you already have · Voice AI · Avatar AI · Denti-OS
Two engines
New patients. And the ones sitting in the chart.
Most clinics buy more ads while overdue recare, unsigned plans, and quiet patients sit in the PMS. We run both engines: capture the inquiry you already paid for, and sell the unfinished work you already diagnosed. Same method we use when a business already has years of buyers — refine the list, write the SOPs, then let workflows print the next dollar.
Engine 1 — ingest: website, phone, chat, Avatar AI into one CRM
Engine 2 — the chart: recare, unaccepted treatment, inactive patients, finished-ortho / family
Neither engine is a blast to the whole database. Refine first. Then three workflows, not forty campaigns
The list you already have is a gold mine and a landmine. We treat it like both.
Denti-OS ecosystemLive
Engine 1 — the leak
Growth dies between the ad and the chair
You already spend on Google, Invisalign, and a coordinator. Money leaves at lunch, after 5, and overnight: voicemail, a web form until tomorrow, an unconfirmed records visit, a plan with no follow-up. GP or ortho — that is not a branding problem. It is an operating-system problem.
New-patient calls that hit voicemail never become exams or consults
Speed-to-lead in hours, not minutes, kills web inquiries
Unaccepted crowns, implants, perio, or aligner starts sit in a folder instead of a cadence
The practice does not need more ads first. It needs to keep the demand it already bought.
Engine 2 — data you already have
The money is already in the chart
A decade of patients is the dental version of a decade of orders. Overdue recare. Plans presented, not started. People who came once and vanished. Ortho cases that finished and never brought a sibling. We do not email “everyone in the PMS.” We refine to the patients who can still be asked — then SOPs and workflows do the asking every time.
Paid or charted truth only — not junk rows, not a Law 25 blast
New ads fill the funnel. The chart you already paid to build is the second funnel.
KPIs · liveLive
The Soshogle Method
Five steps. Both engines.
We do not sell a chatbot and hope. Ingest every inquiry and the chart worth keeping. Codify how YOUR clinic actually works. Benchmark the week against itself. Analyze where production leaked. Refine the playbooks until the loop compounds. Denti-OS is where that loop lands in the chair — dentistry and orthodontics.
Ingest — new leads and the existing patient file into NexRel
Codify — SOPs for recare, unaccepted plans, consult, and start
Benchmark · Analyze · Refine — weekly KPIs, then change the playbook
Marketing fills one engine. Data + SOPs + workflows fill the other.
Revenue MachineLive
01 Ingest
Every inquiry — and the chart — in one place
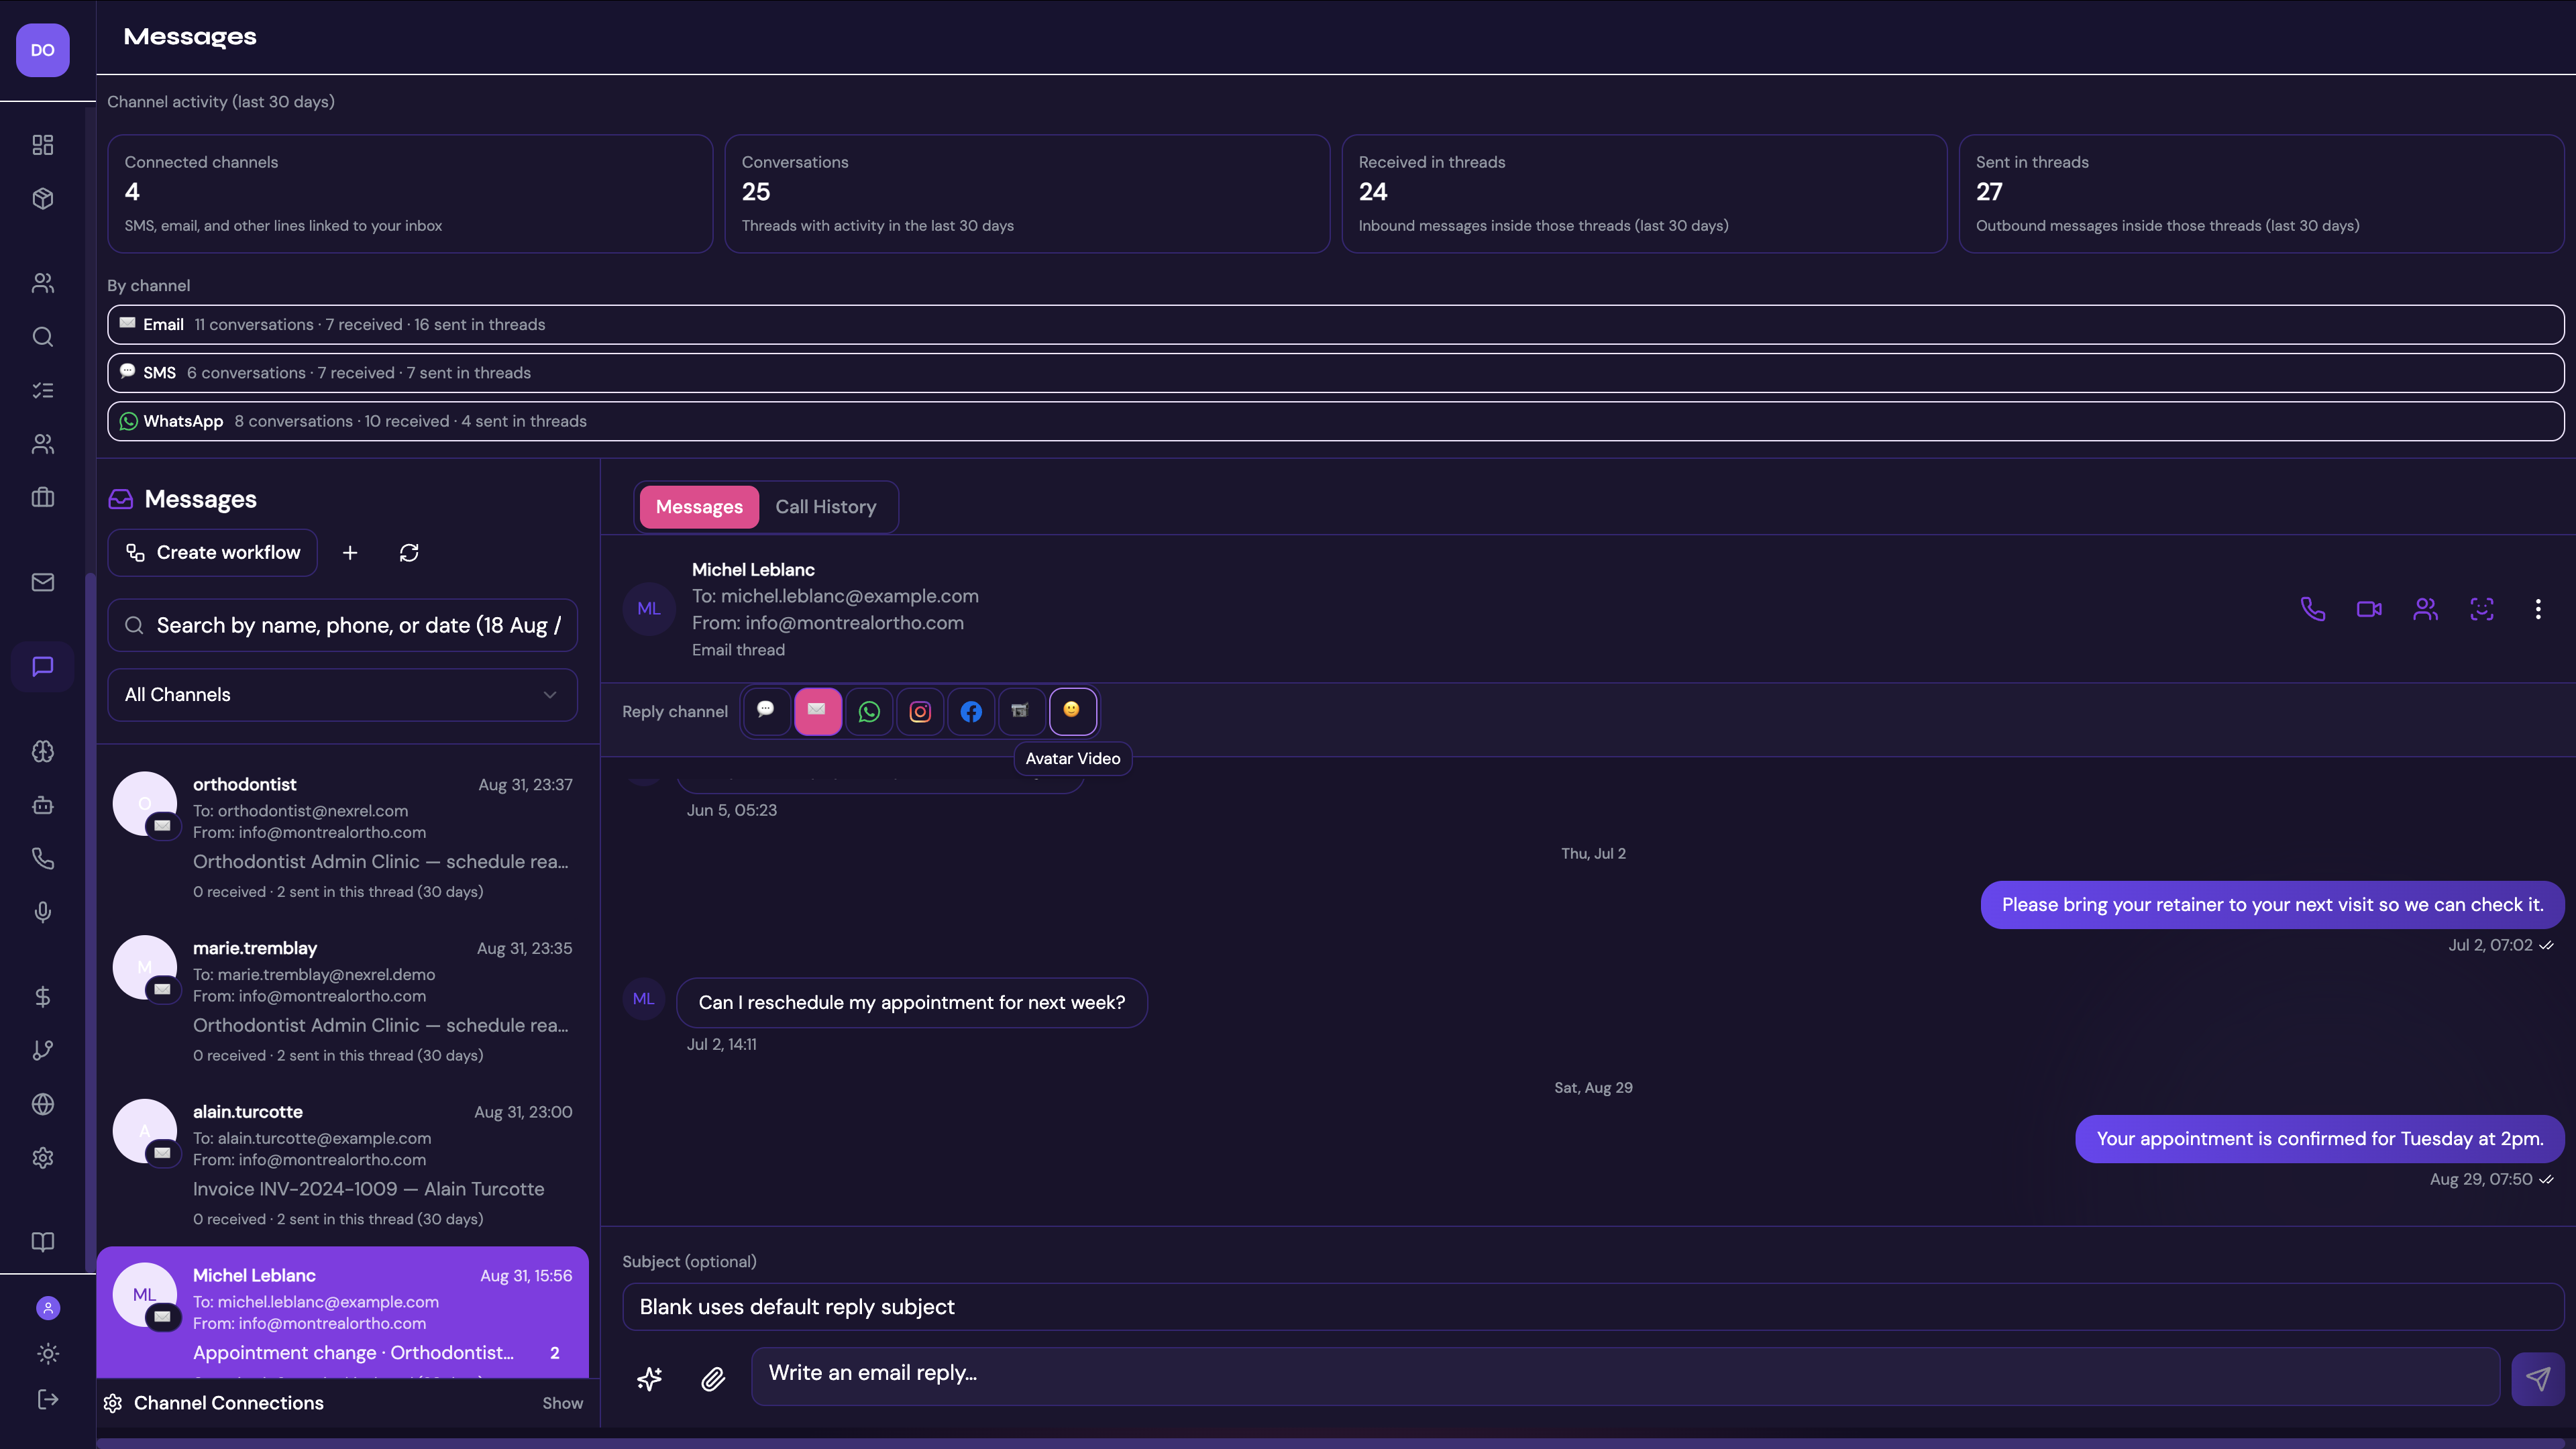
The bilingual AI website, Soshogle Voice AI, Soshogle Avatar AI, and the form write into NexRel. The existing patient file comes in as the second ingest: recare due, plans sitting, last-visit dates. If it is a person you can still treat, it is a record with a next action — not a spreadsheet on a coordinator’s desktop.
AI website books in French and English
Voice AI covers lunch, evenings, and overflow
Chart fields that pay: last visit, plan status, recare due, unaccepted codes
If it is not in the CRM, it cannot be in a workflow.
Refine the data
Clean the list before you sell it
A raw PMS dump is how you burn Law 25 goodwill and the brand in one weekend. Campaigns use patients who are still yours to contact: due, overdue, plan presented, or lapsed with a real last visit — not deceased flags, not junk emails, not “everyone since 2014.” After the refine we report unique contactable patients by segment. Then we write rules. Then we enroll.
Source of truth: the clinical chart / Denti-OS record — not a marketing CSV
Suppress: no consent, bounced, deceased, active-in-chair this week
Score the pool first. No promo until the segment counts exist
Refine is the gate. Same rule as a store with ten years of orders: paid/charted truth, then talk.
KPIs · liveLive
Segments that pay
GP and ortho — different gold, same machine
We slice the chart the way we slice a buyer list: who already said yes once, who went quiet, who has unfinished work. The labels change by specialty. The discipline does not.
High ticket stays a human task. Automation does not diagnose
Highest close rate is unfinished work on a patient who already trusts you.
KPIs · liveLive
02 Codify — SOPs
How you sell, written once
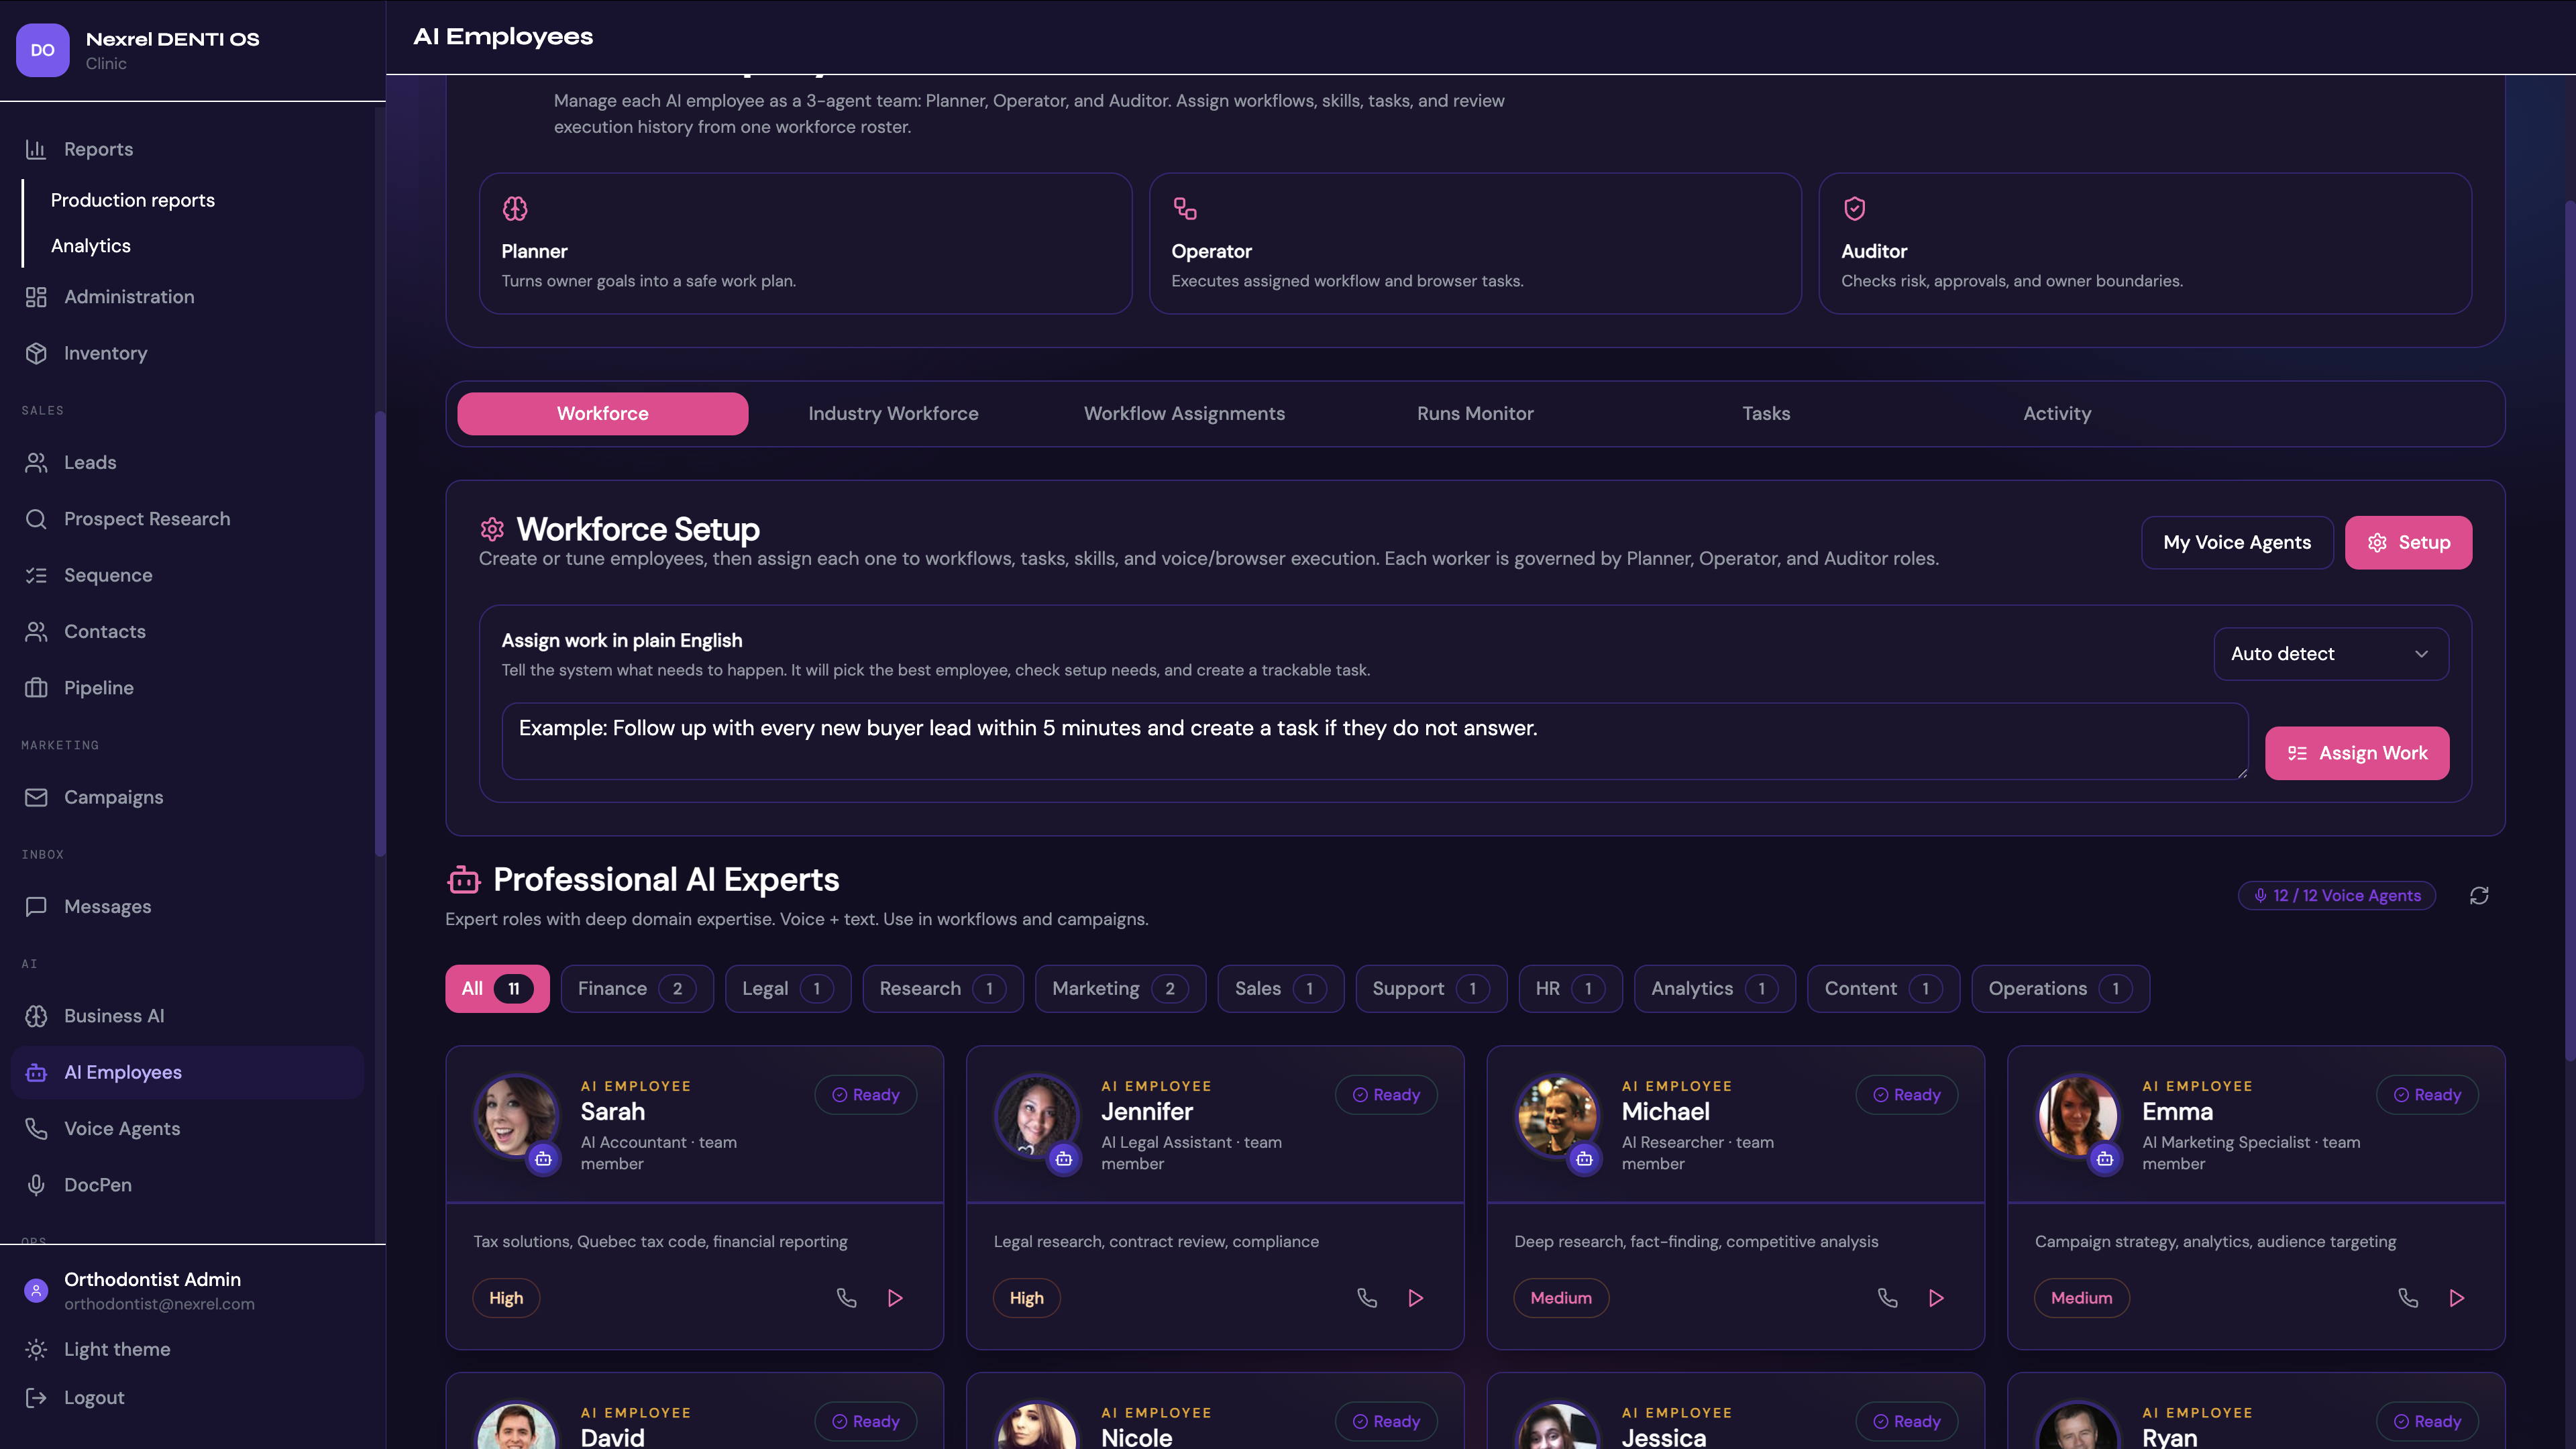
How recare is offered, when a plan gets a 48-hour follow-up, when the doctor must speak, what Voice AI is allowed to book — that lives in one coordinator’s head until we write it into NexRel. Then the AI employees and the floor run the same cards.
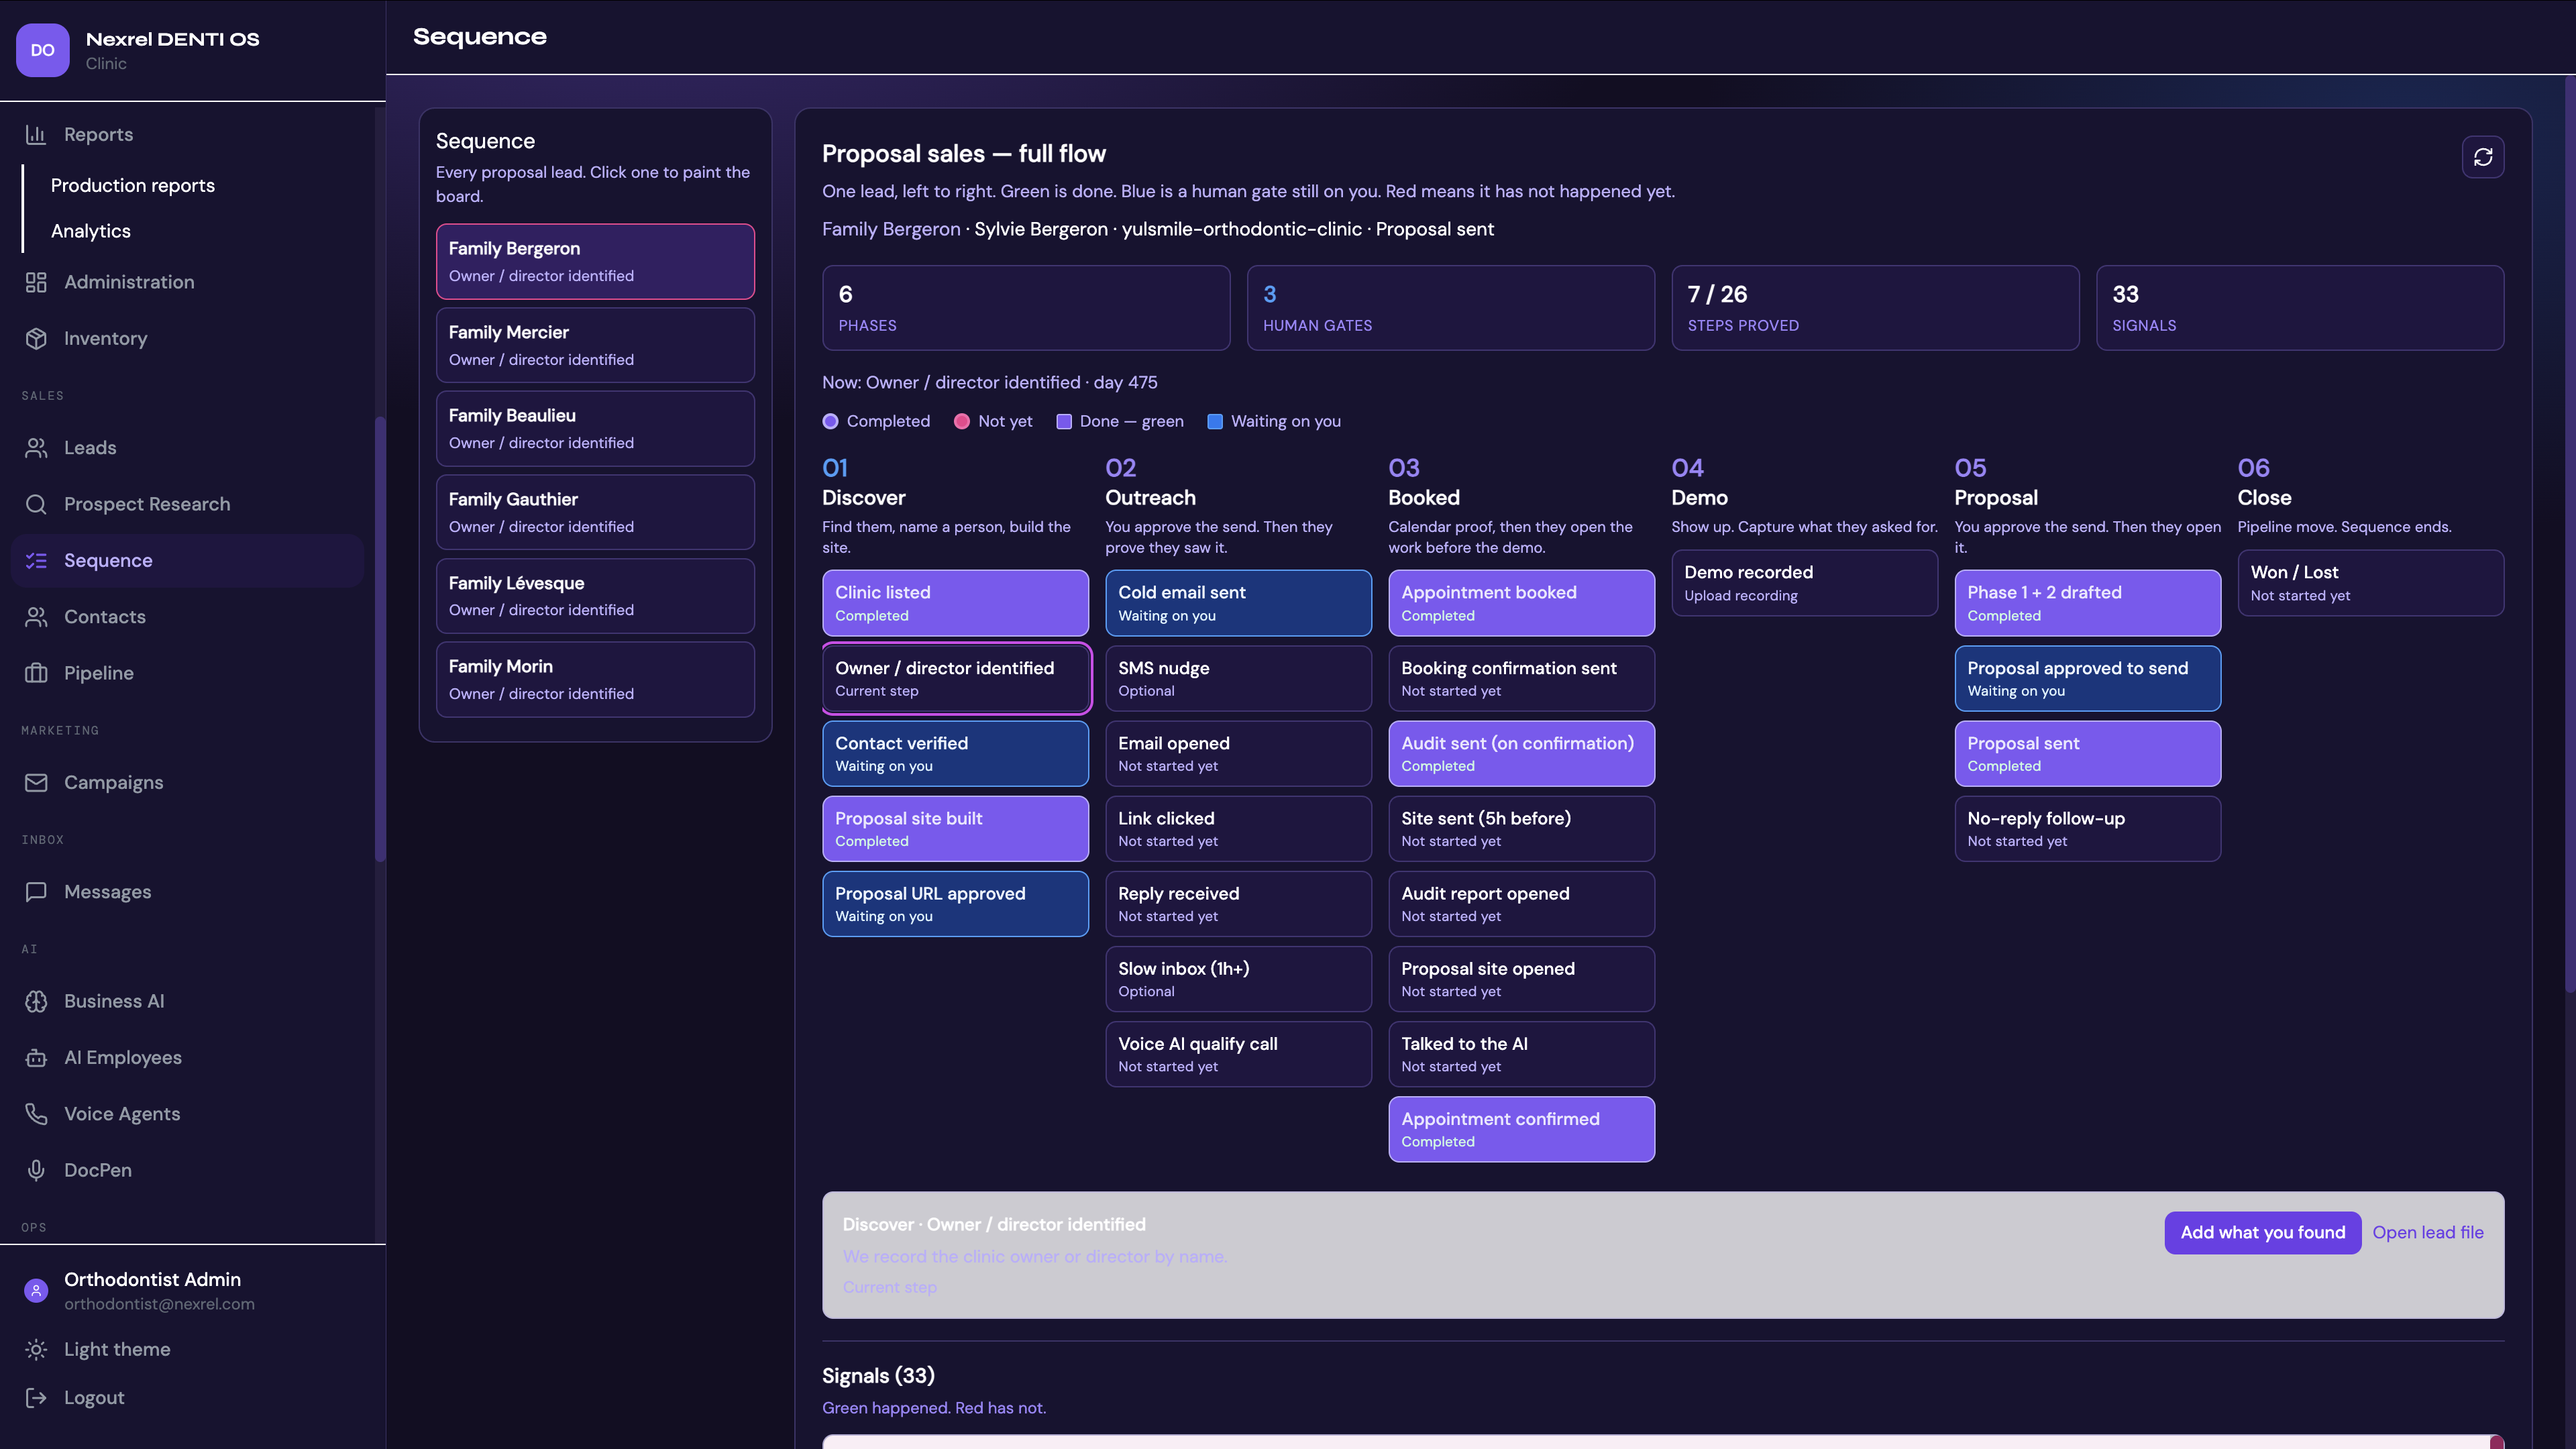
SOP cards: recare · unaccepted plan · new patient / consult · human gate · voice/chat
Same playbook for Soshogle Voice AI, Avatar AI, and the desk
No campaign copy until the cards exist — the SOP is the if-this-then-that
Workflows execute SOPs. Campaigns fill the calendar. Guesswork is not a third option.
Workflows that make money
Three live workflows. That is the cap.
Year one is not forty zaps. Three workflows, same shape as a store that already has buyers: thank-you and next step on a completed visit, recover what was left unsigned, win back who went quiet. Sequences exit when they book or start — they do not nag forever.
Recare due / overdue — reminder, offer, then stop or hand to the desk
Plan presented, not started — 48-hour then 7-day follow-up, then a human
Quiet 12–36 months — one win-back sequence, then suppress
Ops, not ads. The workflow fires every time. A sticky note does not.
NexRel workflowsLive
Campaigns & nurture
Three live. No more.
Email and SMS already enroll on triggers. For a dental or ortho practice we run three campaigns on the refined list — not a weekly promo to the whole chart. Nurture is slow education for one-and-done. Voice and SMS only where consented and high-ticket.
Recare cadence — due and overdue only
Unaccepted treatment / unsigned start — one SKU path, then stop
Inactive / finished-ortho / family — win-back once, then rest
Done means a booked chair or a start in the OS — not an open rate.
03 Benchmark
Score the week against itself
Week one we instrument YOUR phones, forms, recare due, unaccepted plans, and starts. The benchmark is your clinic — not another city’s average, not a retail million pasted onto dentistry, not a brochure number from a clinic we have not gone live with.
Capture baseline: missed calls, speed-to-lead, consults / new exams
Chart baseline: overdue recare count, unaccepted $ sitting, inactive pool
Starts and production vs last week — GP and ortho on the same board
No KPI is real until it is your number, from your week.
KPIs · liveLive
04 Analyze
See which step dropped the dollar
A slow month is not a mystery when the OS shows: 11 after-hours calls, 2 forms untouched 14 hours, 180 overdue recare, 28 unsigned plans, 3 aligner starts with zero follow-up. Analysis is the leak map for both engines.
Where new inquiries die: phone, web, chat, or no follow-up
Where existing production sits: recare, plans, inactive
Coordinator load vs after-hours coverage vs list size
You cannot refine what you cannot see.
Revenue MachineLive
05 Refine
Change the playbook. Repeat.
Faster lead response. Auto-confirm. A recare workflow that actually fires. A 48-hour plan follow-up. Each change is a SOP plus an automation — next week’s benchmark says if it paid. The loop never ends at go-live.
Automations fire every time — not when someone remembers
Keep what moved chairs and starts, kill what did not
Do not add a fourth blast because the third felt busy
Growth is a weekly operating rhythm, not a website launch.
Scoreboard
The KPIs we put on the wall
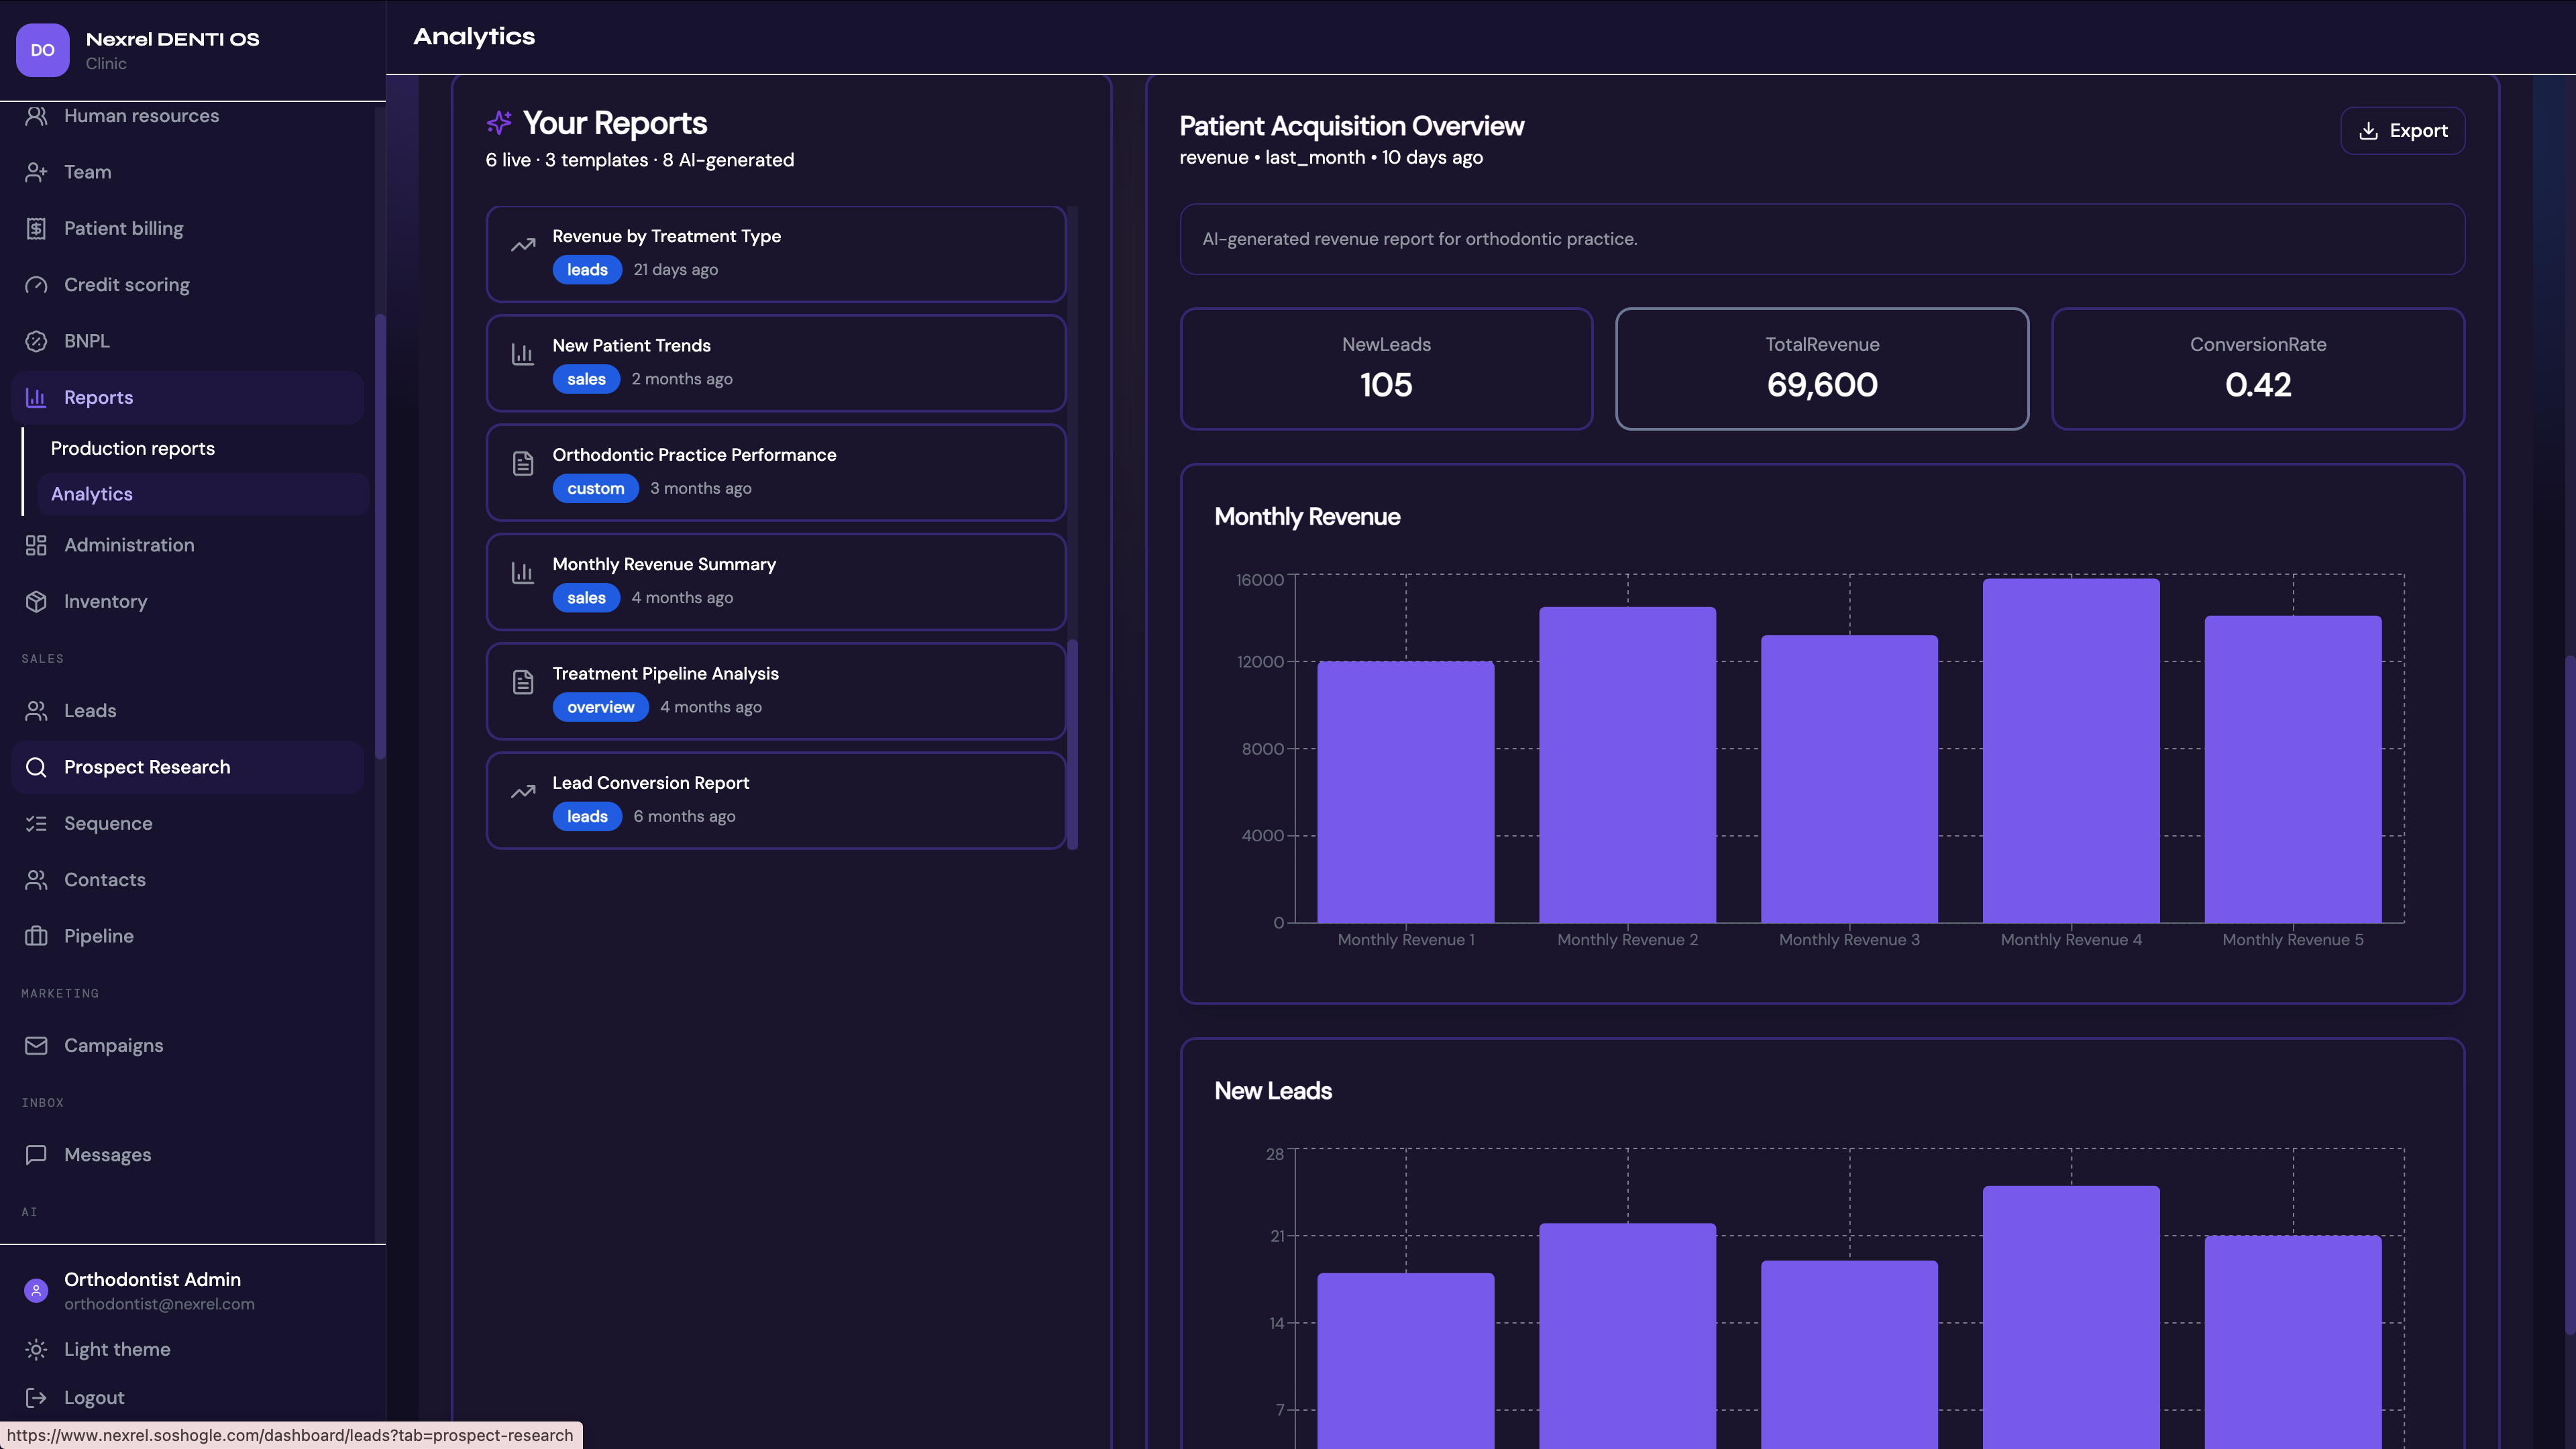
Numbers that predict next quarter’s production — not Instagram likes. Doctor, coordinator, and AI employees look at the same board. GP and ortho share the capture KPIs; specialty KPIs sit beside them.
Plans: 2 unaccepted new starts/month × 10% extra close × $5,500 ≈ $13k CAD/year
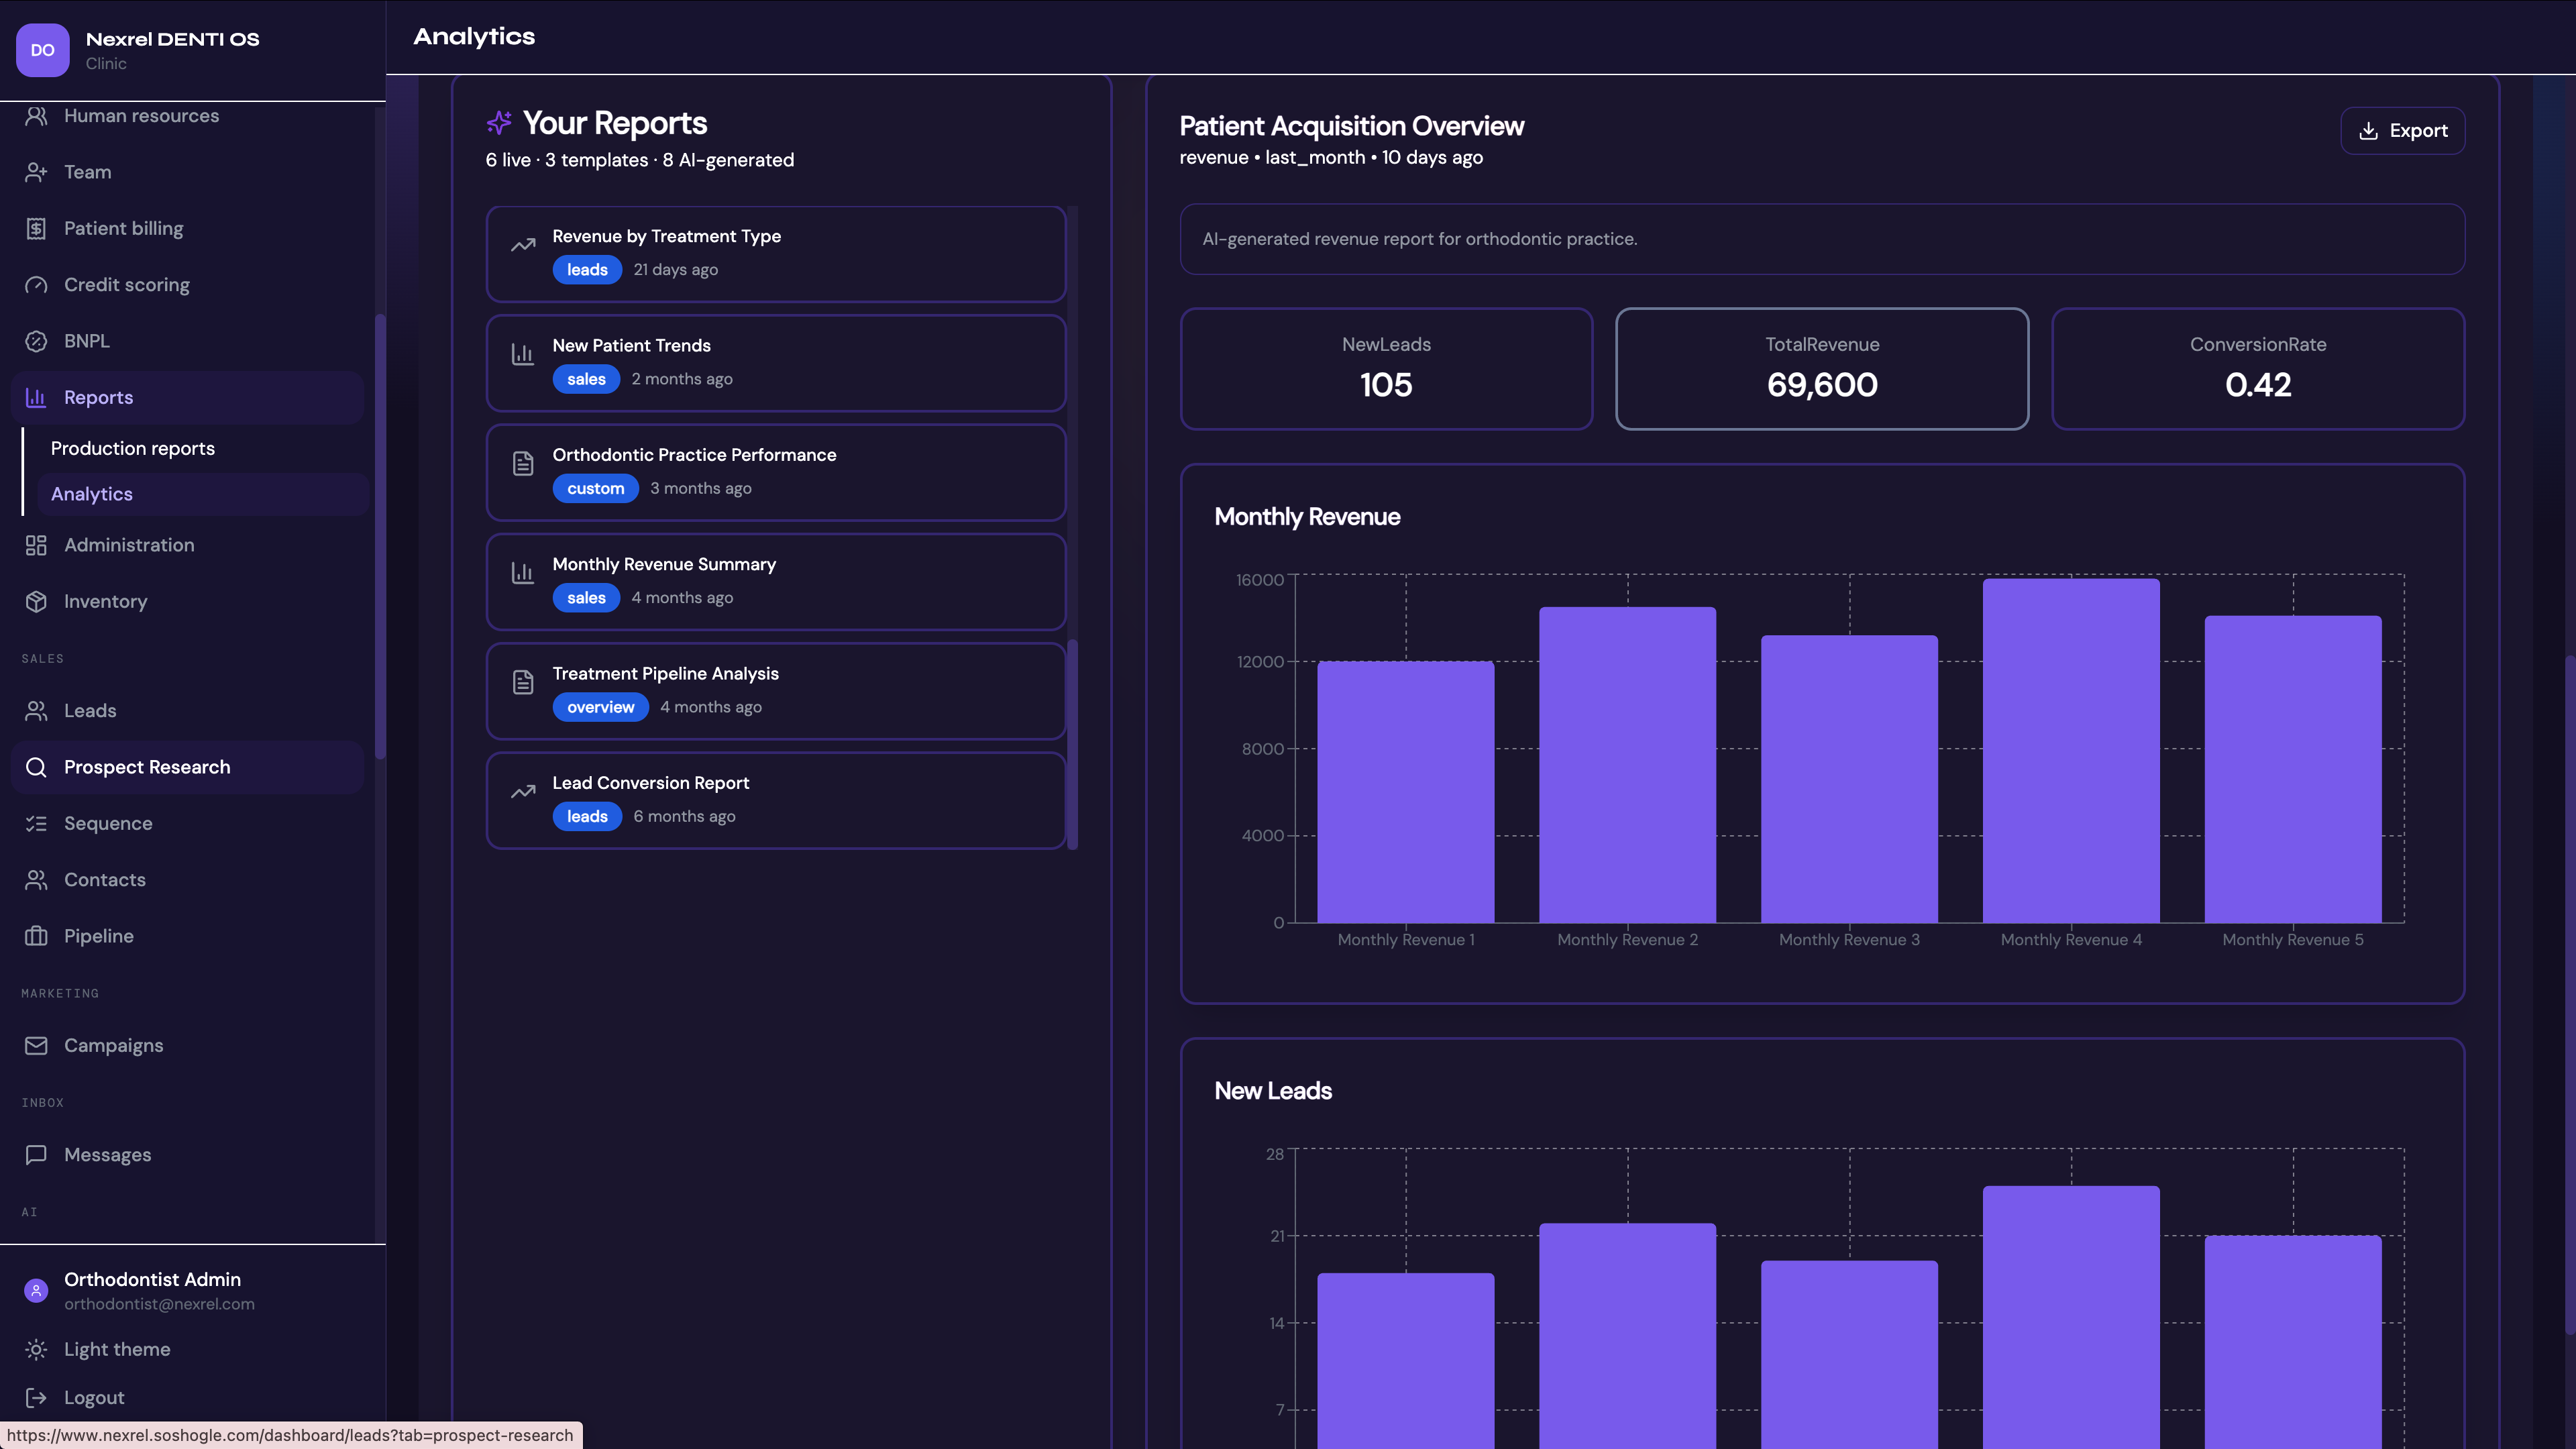
Modeled ~$50–70k CAD year-one from capture + follow-up on conservative inputs. Not a 4× client result.
Modeled ROI — engine 2
Conservative math on the chart you already have
Same idea as turning years of orders into added sales — here the “orders” are unfinished dentistry. This is a working model for a busy 1-location practice, not a guarantee and not a retail $1M pasted onto a dental chart we have not counted. Multi-site and a fat unaccepted book scale from your refine report.
Done is a kept recare or a start in Denti-OS — not an email open
Modeled ~$80–150k CAD year-one from existing patients on conservative 1-location inputs. We do not claim a million until your segment counts say the pool is there.
What we do — the door
The AI website that books dentistry
Bilingual, LLM-discoverable clinic site: real hours, real phone, booking, chat into NexRel. GP, specialty, or Invisalign story — the site is the ingest layer, not a PDF.
French + English, Law 25-aware intake, hours and map that match the clinic
Online exam / consult / first-visit booking into the same CRM as the phone
Soshogle Avatar AI on the page for the questions patients ask at 21:40
The website earns its keep when a midnight question becomes a Tuesday chair.
Ads IntelLive
What we do — the line
Soshogle Voice AI never puts the practice on hold
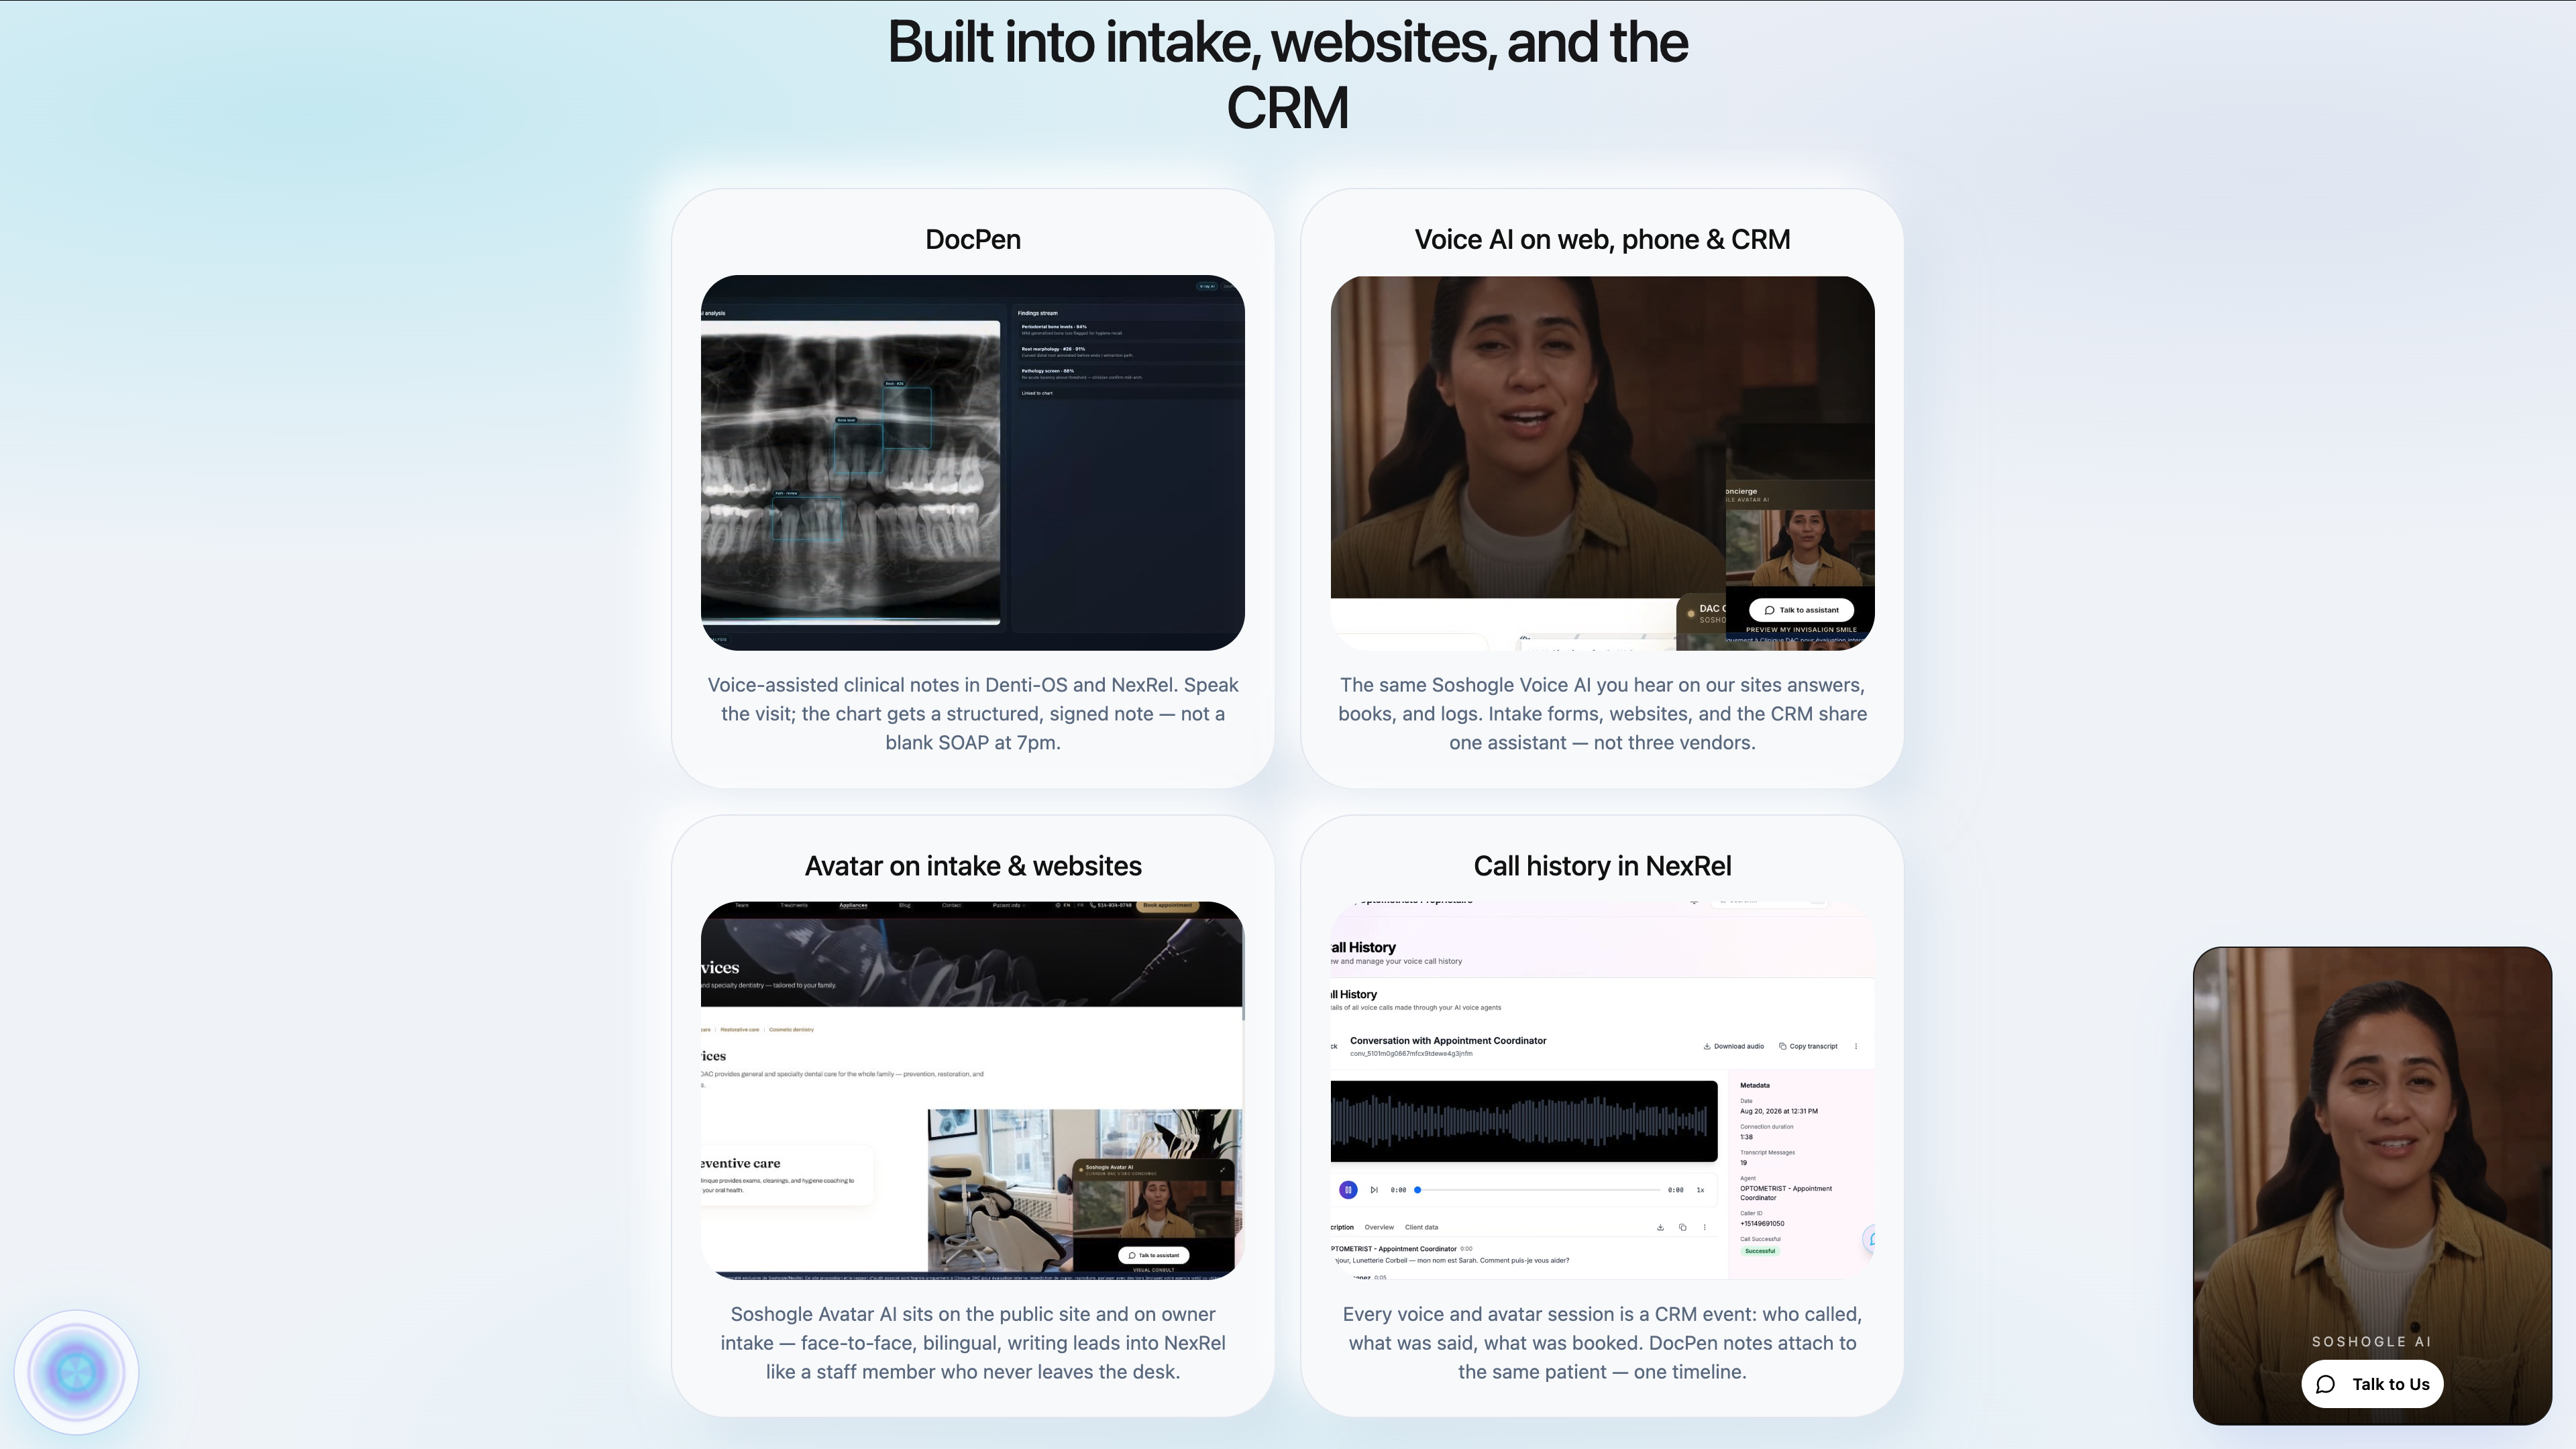
Lunch, evenings, every coordinator at the desk — that is when new-patient calls die. Voice AI answers, qualifies, offers the exam or consult, pushes a lead. Humans take the clinical questions. The OS keeps the log.
After-hours and overflow in FR/EN
New vs existing vs emergency, with a next step
Every conversation a CRM record — not a voicemail
The most expensive ad this month is the call nobody answered.
Soshogle Voice AILive
What we do — the floor
Denti-OS is where the start happens
Once the visit is booked, the machine has to survive the chair: agenda, recare, treatment plan, notes, billing. Denti-OS is the dentistry and orthodontics OS on NexRel — so growth workflows and clinical work are not two vendors.
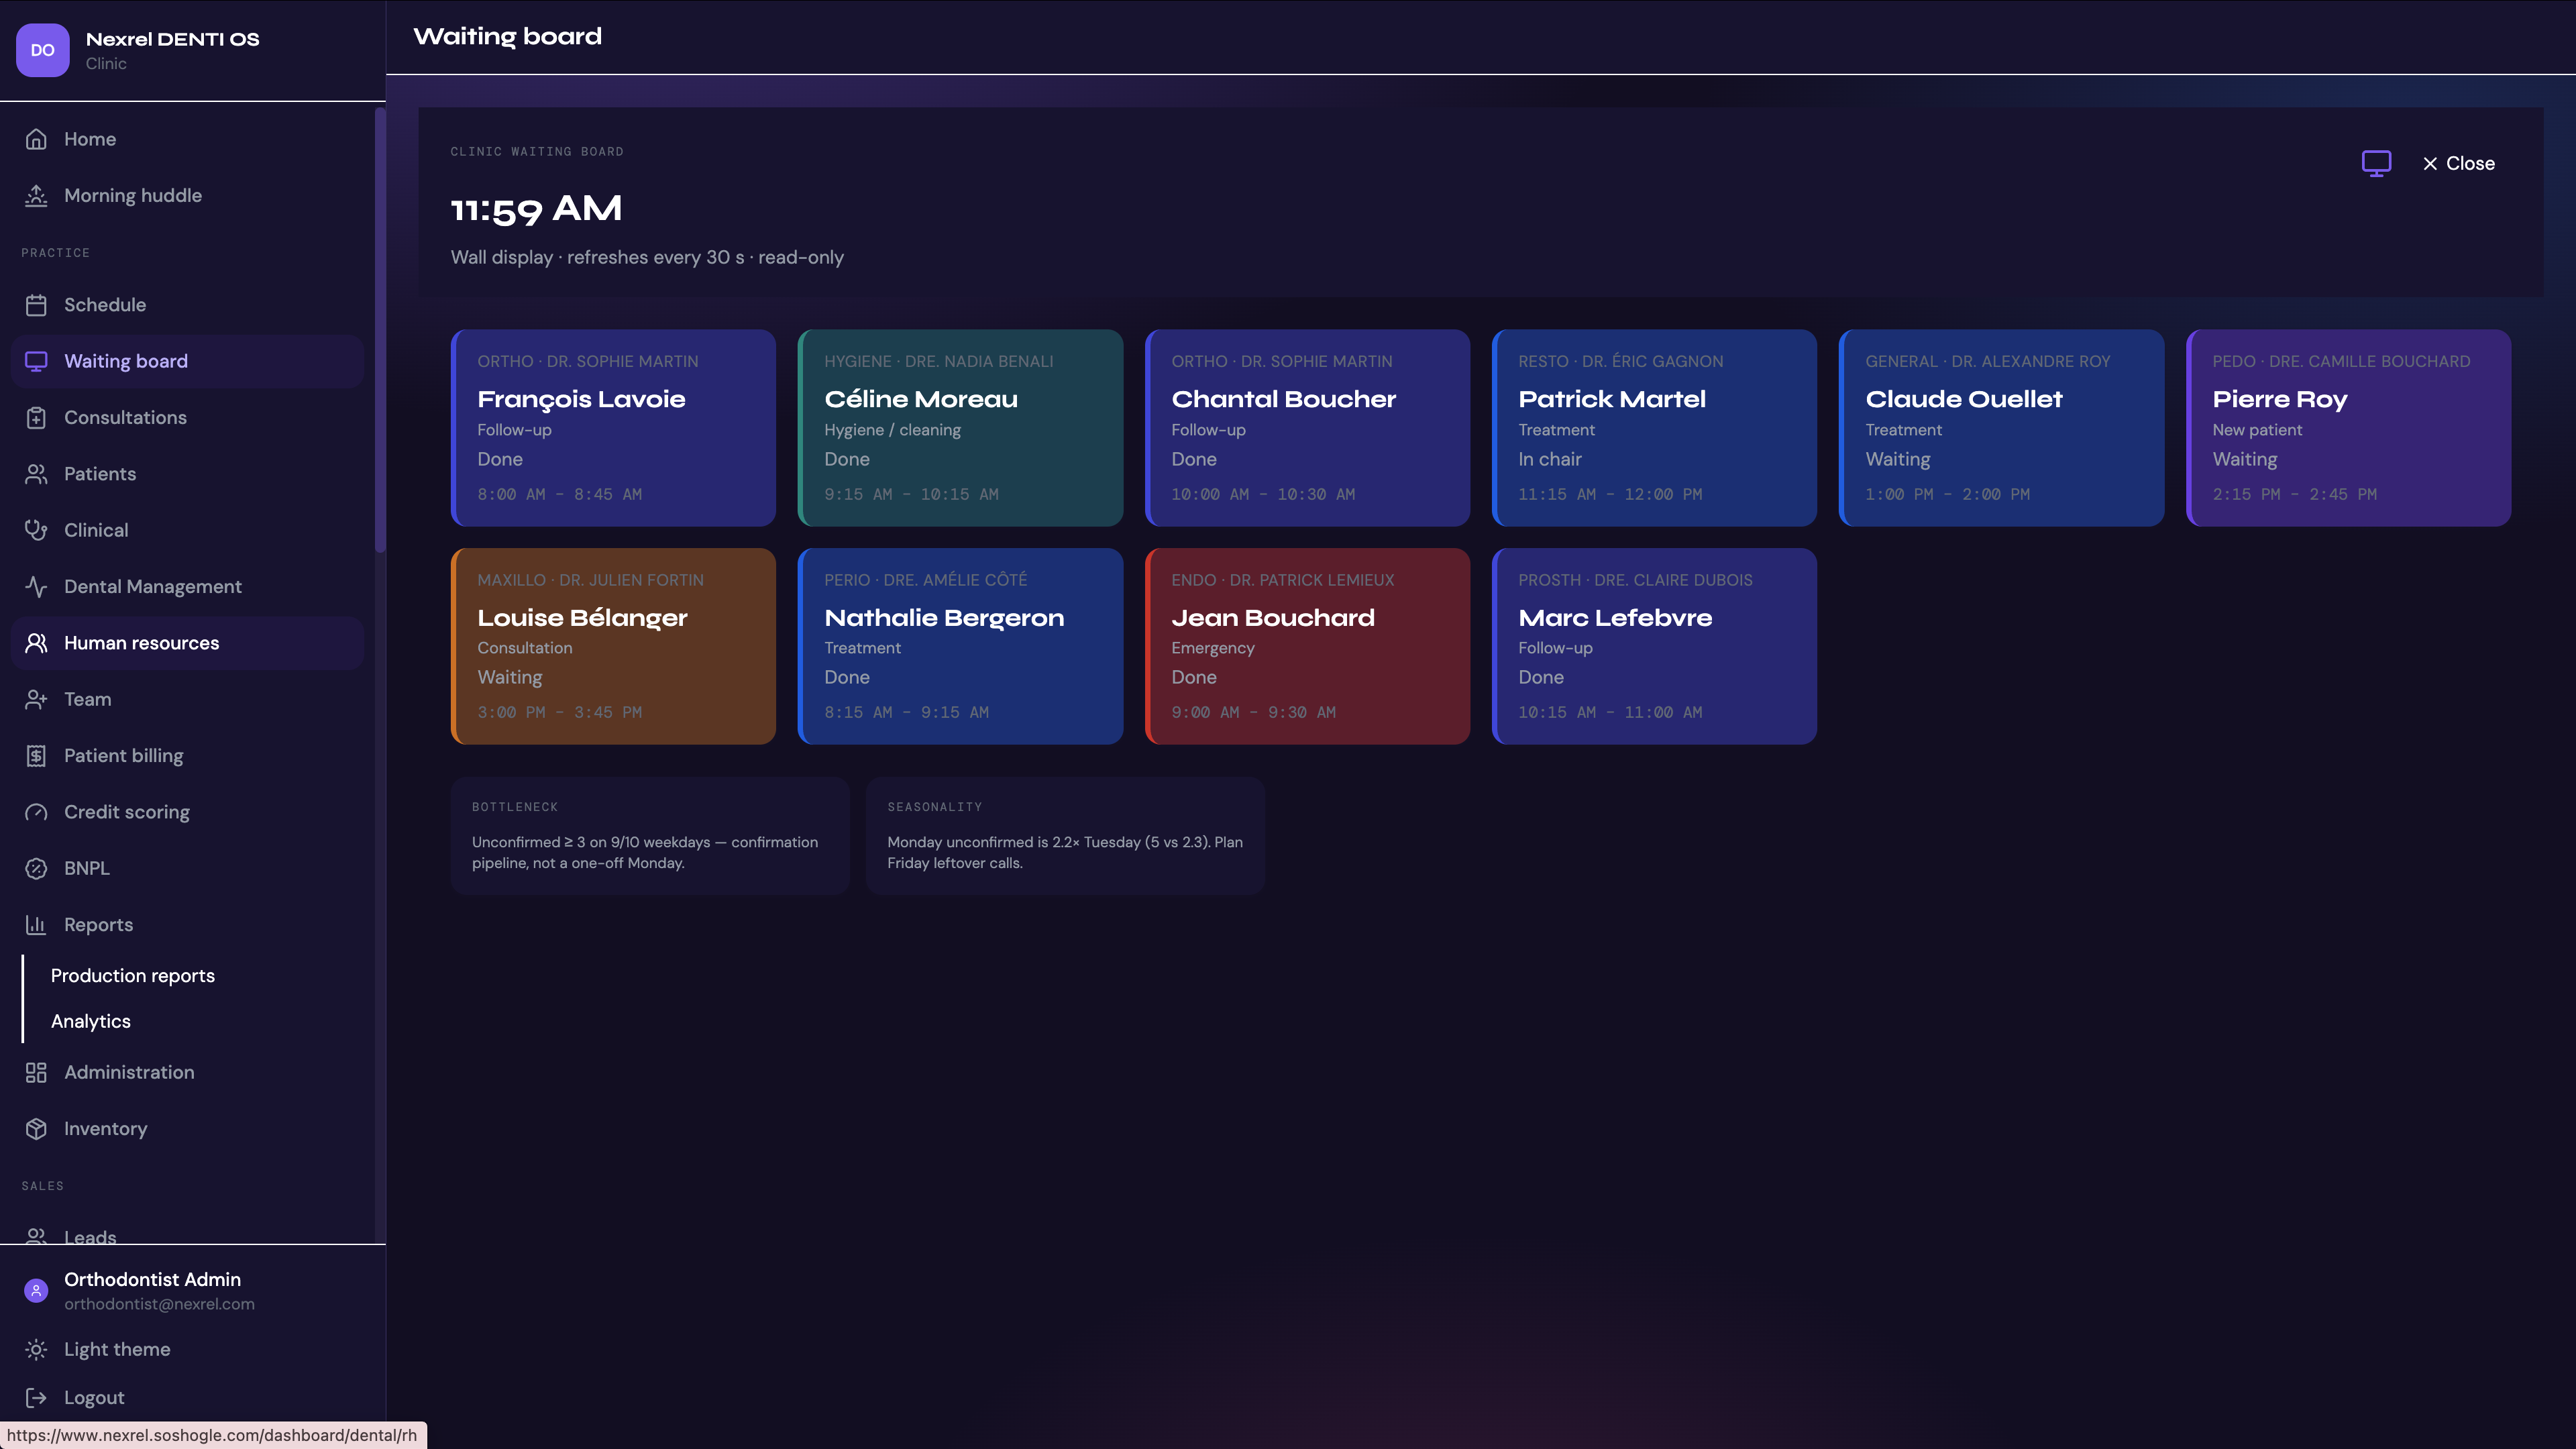
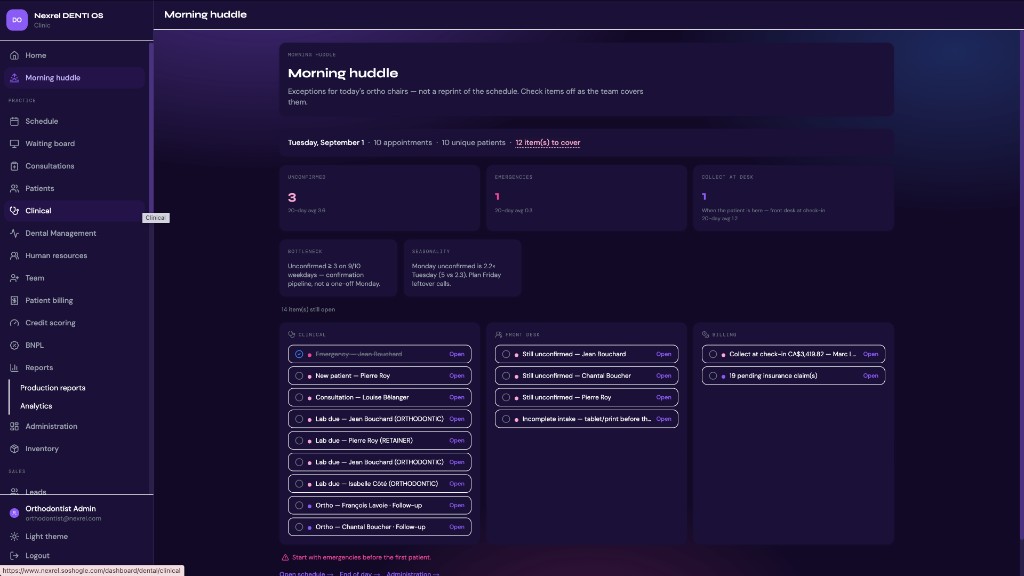
Multi-chair agenda, recalls, live floor
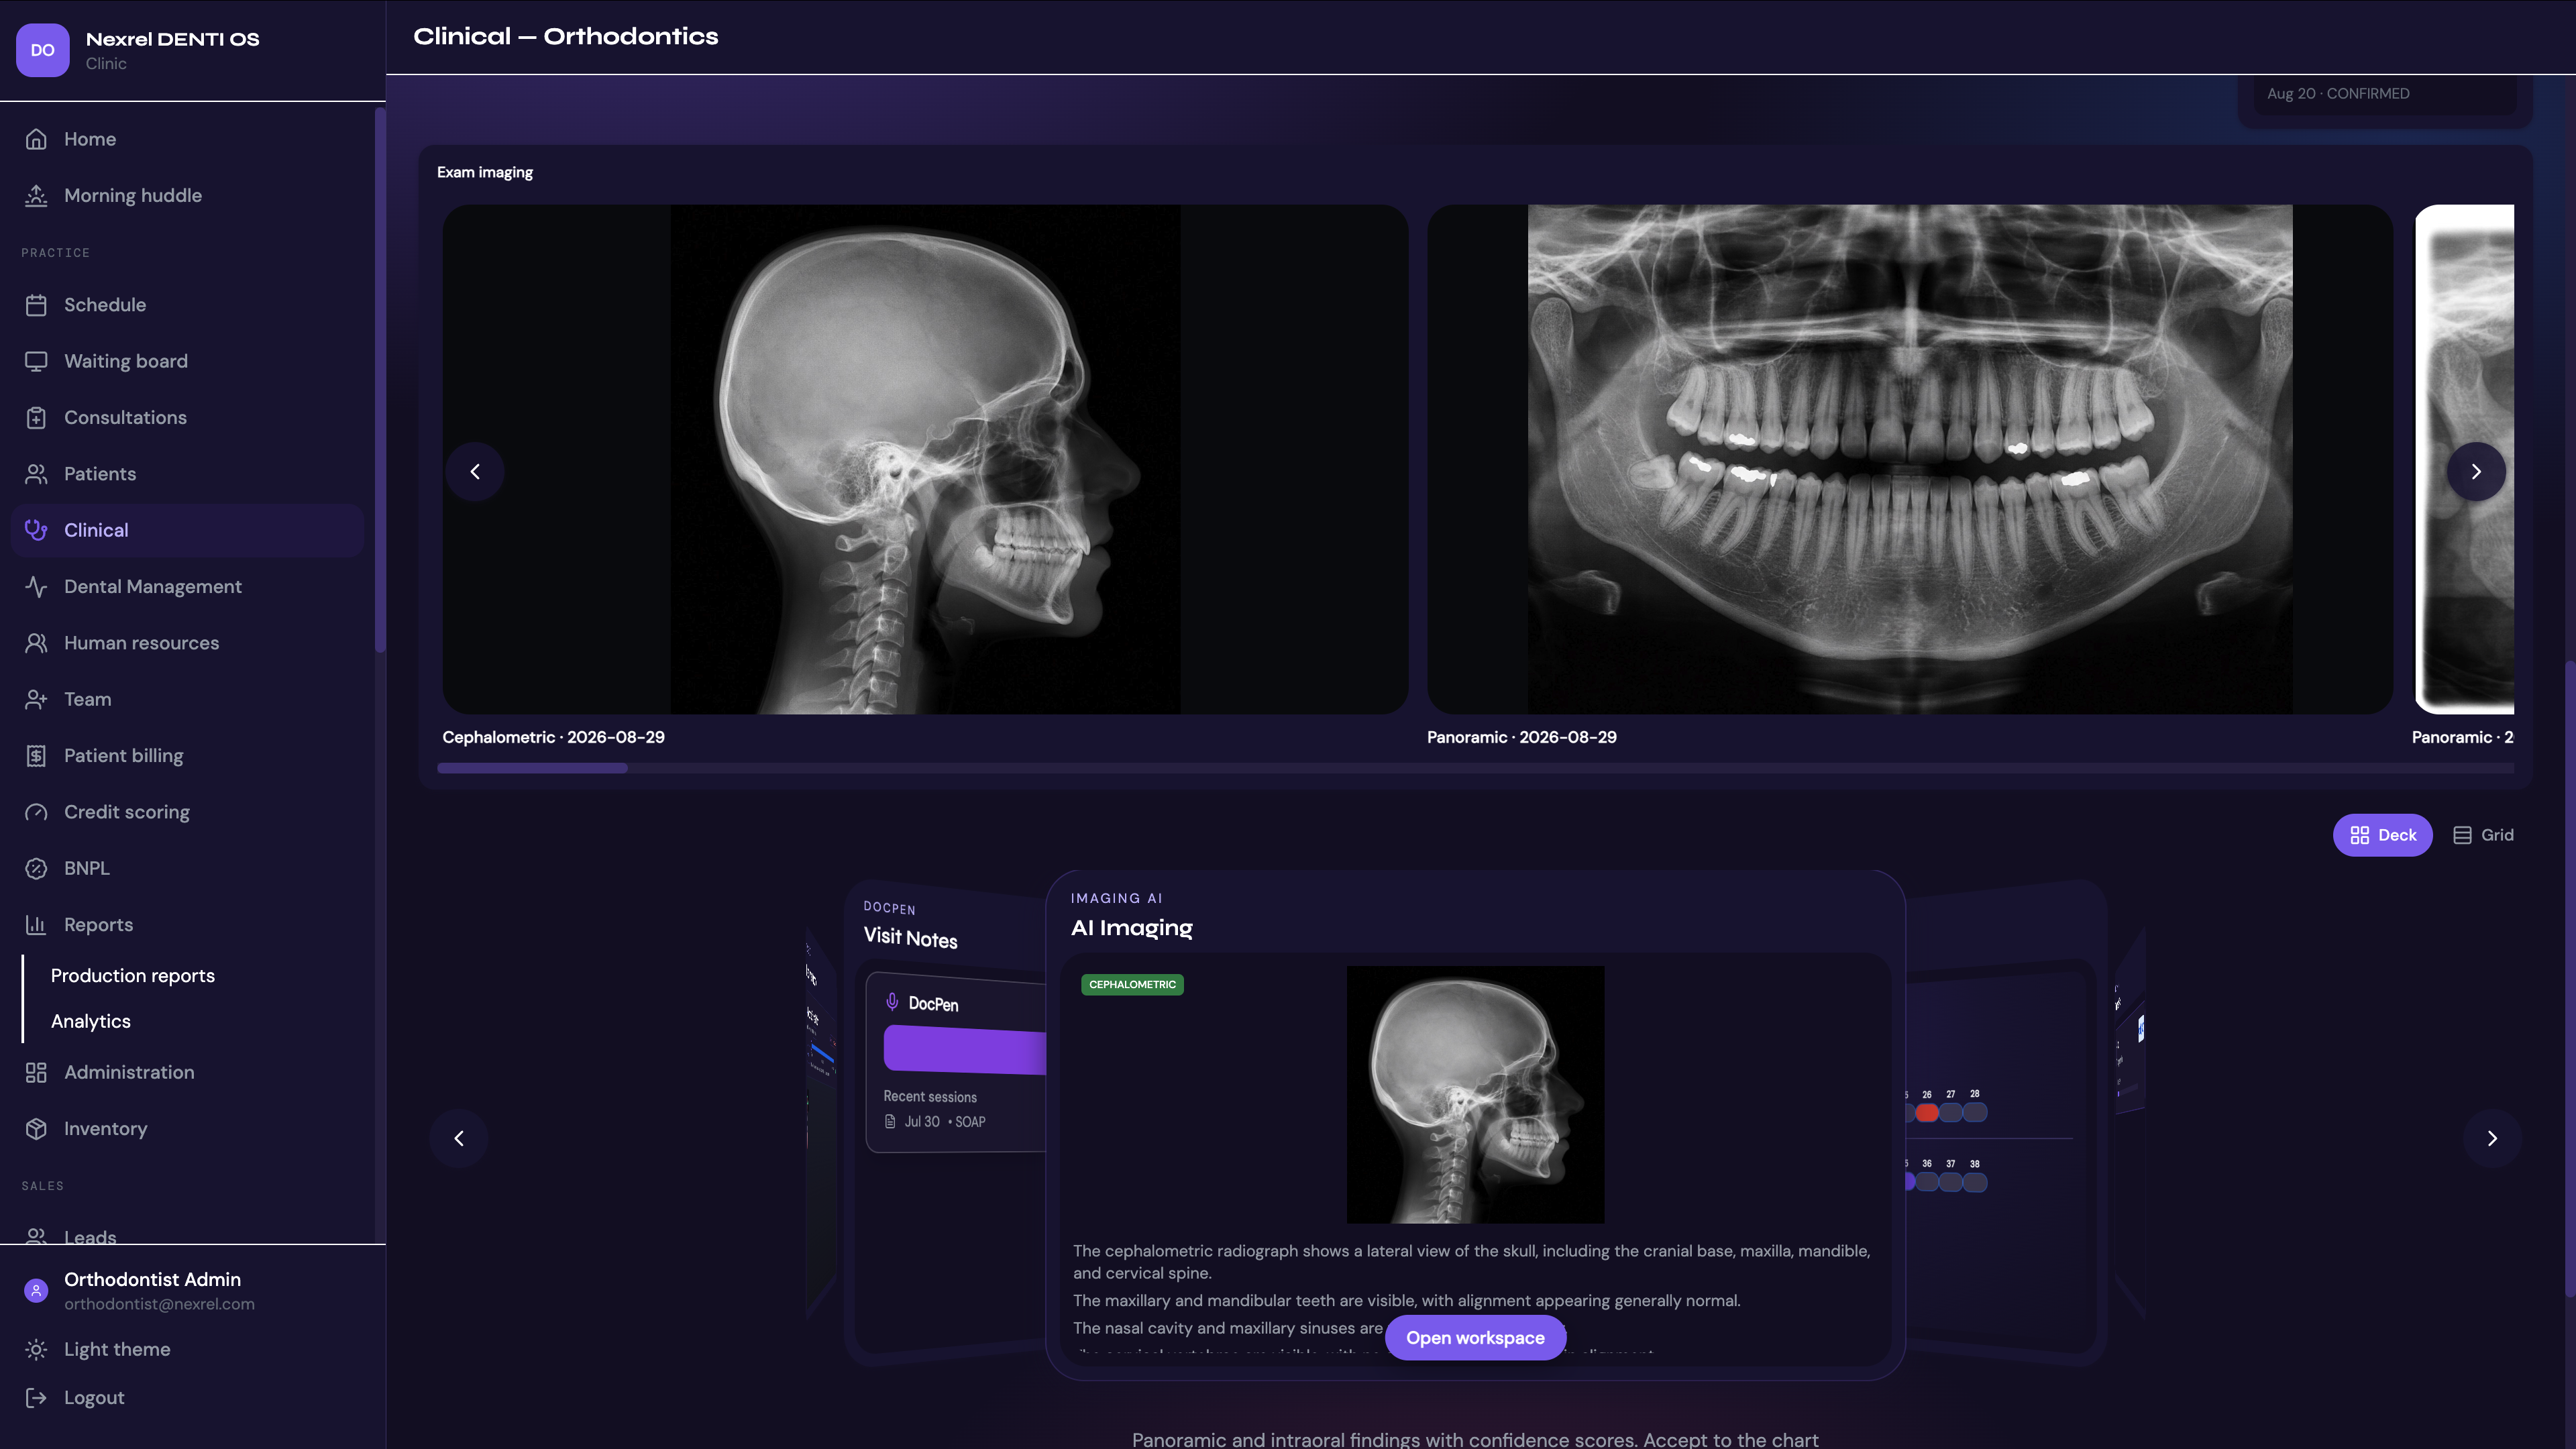
DocPen notes and charting tied to the same patient the campaign just booked
KPI board the doctor can open between chairs
A booked recare that dies in a disconnected PMS is still a leak.
What we do — GP and ortho
Unfinished dentistry. Long ortho cycles.
GPs lose money in unsigned restorative and overdue hygiene. Ortho loses it in the middle: plans presented, not started; patients quiet at month four; retention nobody owns. We encode both specialty loops so the AI employees run your practice type — not a generic blast.
GP: recare + plan-presented cadences as automations
Ortho: consult → start, Invisalign progress, family / retention as production
Human gate when the ticket is clinical, custom, or a complaint
Ortho is 18–24 months. Recare is forever. The OS has to last that long.
What we will not do
Don’t burn the chart
Same discipline as a buyer list with a decade of history: we will not enroll the raw PMS dump, SMS people without consent, or call a campaign done because emails opened. Québec practices get Loi 25-aware intake and suppress. Done means a kept chair or a start.
No blast to every email in the legacy software
We will not invent a million-dollar result or a 4× return for your clinic
High-ticket and clinical questions are tasks to a human
Trust is the first KPI with a dentist. We will not spend it.
Year one
Twelve months, in order
Nothing enrolls until you say go. Month 1 is the refine report — contactable patients by segment — and the SOP cards. Then three workflows. Then one campaign with a cap. We score the year on chairs and starts in Denti-OS.
Month 1: refine the chart, segment counts, SOP cards, no promo
Month 2: three workflows + one recare or win-back campaign, kill switch on
Months 3–12: unaccepted-plan cadence, inactive once, tune from production not opens
This booklet is the plan. The refine report is what lets us contact your patients.
Next step
Bring the leak and the list
Bring last week’s missed calls, overdue recare count, and how unsigned plans actually get followed up. We walk both engines — new demand and the chart you already have — for GP, ortho, or both. 20 minutes. Then the KPI board we would hang first.
Discovery call with Soshogle — dentistry and orthodontics
Clinic OS booklet at denti-os.com/brochure for the full product tour
Founding-clinic beta: we instrument your baseline; we do not fake the scoreboard
Book the call. Bring the chart. We will show the machine.